Author Archives: Arlen Meyers

About Arlen Meyers

Arlen Meyers, MD, MBA is an emeritus professor at the University of Colorado School of Medicine, an instructor at the University of Colorado-Denver Business School and cofounding President and CEO of the Society of Physician Entrepreneurs at www.sopenet.org. Follow along onSubstack.

Finding the Right Physician Advisor for a Healthcare Startup

Finding the Right Physician Advisor for a Healthcare Startup

GUEST POST from Arlen Meyers

It has never been easier to create a sickcare startup, particularly in digital health. Part of that process requires that founders find the right players to be on the team. In many instances, that will involve finding physician advisors or consultants.

But, how do you find the right physician advisors?

Here are some tips:

  1. Clearly define the optimal candidate by writing a job description that includes the knowledge, skills, attitudes and competencies you want. Are you looking for someone with an entrepreneurial mindset or someone with just domain expertise? One expert suggests that they should be able to communicate a deep understanding of their domain effectively and understand the context of both their organizations and those they work with. Moreover, emotional competence is essential to developing strong interpersonal skills and succeeding in any workplace. Professionals should also strive to be effective teachers and build a large network of human connections. Finally, possessing an ethical compass will be important as algorithm-driven machines begin to make morally weighted decisions.
  2. Look for past experience and results
  3. Decide how much and what kind of compensation you are prepared to offer, either in cash, equity or both
  4. Make it clear how long you want to engage your advisor. Is it for one hour or one year or more? Or, maybe it’s best to try before you buy and hire for a renewable three-month term.
  5. Clearly define your expectations, deliverables and timelines and how you will measure the results. What roles, holes and goals do you want your advisor to fill?
  6. Solicit candidates using networks, social media channels, word of mouth referrals or responses to a call to action on your website or other marketing collateral
  7. Screen candidates using the criteria you have defined
  8. Decide whether you want someone to fill a business or clinical advisory position. Finding a clinical business advisor is difficult since few doctors or other healthcare professionals have both a clinical and entrepreneurial mindset and the knowledge, skills, abilities and competencies to help you achieve your next critical success endpoints.
  9. Agree on whether you are hiring for periodic strategic input or more tactical, hands-on execution.
  10. Interview candidates to see if they comply with your requirements and whether they are the right fit
  11. Negotiate an agreement
  12. Execute an advisory services agreement that defines the terms and conditions of the relationship

Finding the right physician advisors is an important part of recruiting your startup team. Don’t hire someone simply because of the initials after their name.

Image credits: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Problem Seeking 101

Problem Seeking 101 Charles Kettering

GUEST POST from Arlen Meyers

When federal agencies in charge of protecting Americans’ health recommended that there should be a pause in the administration of the Johnson & Johnson (J&J) COVID-19 vaccine, state health leaders listened and suspended its use. People may experience a mild headache after vaccination. The headaches associated with the blood clot occur one to three weeks after the shot and are more severe.

One expert recommended asking patients, “Is this like headaches you’ve had before? Or is the quality of the headache something that you’ve never experienced before?”

The 12 steps to biomedical innovation starts with being a problem seeker, not a problem solver. Eventually, to be successful, customer problems and solutions need to meld around a VAST business model i.e. one that is not just profitable, but that demonstrates:

1. Validity Regardless or which elements of your model you choose, they have to be valid. In other words, the dogs have to eat the food. When the dog won’t eat the food, you’ll have to change your approach and try again.

2. Automaticity At the very start of planning your venture, you should think about how you are going to work on your business, not in it. Reducing hands on time to manage operations will give you more time to lead the company and create strategies for growth and give you more personal time to enjoy the fruits of your success. Outsourcing, automating or using technologies to ramp up operations, sourcing and distribution is a key part of scaling, and something that investors want to see…which brings us to the next piece.

3. Scalability Your business model is primarily a way to create a business machine that can produce an infinite number of products. Think of it as a device that takes in customers and creates profits out the other end and can do so at quicker and quicker speeds.

4. Time and Traction Finally, your model need to create as much profit as quickly as possible with a growing customer base that is loyal to your brand.

Many doctors, scientists and engineers start with solutions looking for a problem. Some find it or, eventually, as their inventions or technology evolves, markets appear to those who have the talent to see them. The more typical model, and one that is more common among the startup community, is to find a problem and devise a solution.

But, how do you pick the IDEAL opportunity given the almost infinite possibilities? Here are some tips:

I Identify the problem: Seeing a problem is an important skill and core competency of savvy entrepreneurs. It typically is the result of personal experience, primary research talking or watching others or secondary research. Whichever problem you pick, look for ones that:

  1. Will make a very big difference in people’s lives if you solve it
  2. Has the potential to be very profitable or create lots of user defined value, typically at least 10x the value compared to existing offerings or the status quo.
  3. Is something that taps into your passion or satisfies your psychic need
  4. Anticipates future customer/stakeholder wants and needs
  5. Has an extremely high level of market pain and frustration, where customers know they have a problem and have unsuccessfully and repeatedly tried to solve it
  6. Has limited barriers to entry
  7. Has the right potential risk-return profile that matches yours
  8. Is not one dominated by incumbents
  9. Is easy to explain and understand
  10. Someone is willing to pay enough for your solution so that you can make it profitably

Where massive success comes – where a good idea becomes great – is when it meets five simple criteria:

  1. It is the first solution to a problem or gap (it is “innovative”)
  2. It is the first WORKING solution to a problem or gap (it is “innovative and effective”)
  3. It is the most affordable, comparable, option for its market (it is “innovative, effective and affordable”)
  4. It consistently examines its effectiveness and seeks to improve (it is “innovative, effective, affordableand adaptive”)
  5. It is powerful enough to create a loyal following that naturally wants to – and does – share the idea with others (it is “innovative, effective, affordable, adaptive and influential”)

How do you find problems worth solving?

  1. 1. Solve a problem that you already face
  2. 2. Observe a problem and solve it
  3. 3. Anticipate a problem and solve it
  4. 4. Create a problem and solve it
  5. 5. You have a personal stake in solving it
  6. 6. The 3 W’s: Will customers WANT it, is it WORTH it, can you WIN at it?

Identifying a problem starts with identifying a customer archetype that has it. Beyond guessing, identifying that person and describing their problem can only be done by talking to, working with or observing potential customers.

Doctors call it taking a pain history and documenting the chief pain complaint, the history of the present illness and their past medical history. In other words, talk to people and have them describe:

  1. Where is your pain?
  2. How bad is it?
  3. How long have you had it?
  4. On a scale of 1-10, how would you describe it?
  5. What have you done in the past to make it better?
  6. What makes it better or worse?
  7. What other problems do you have that makes the pain better or worse?
  8. How have you treated it in the past?
  9. Is the pain constant or intermittent?
  10. What would you pay to relieve the pain?

Startup geeks call this process customer discovery by “getting out of the building”. Doctors call it making house calls. Here is the ultimate list of customer discovery/development questions.

Here is a customer interview script.

Remote patient programs , for example, don’t just automatically work out. They have to be carefully planned and developed in order to gain traction and produce results. Most importantly, they have to target the right patients.

D Define and represent the problem

Primary or secondary research should give you some idea about :

  1. Market size
  2. Market growth
  3. The competitive landscape
  4. Where you intend to play
  5. What you see that others don’t.

Once you have done these things, then you can:

E Explore and experiment with possible strategies or solutions and risks involved with each by identifying customer segments and creating a value proposition canvas and a business model canvas

Here’s an into to value proposition design

When you create new value propositions and growth you need to focus on high-value customer jobs. These are not necessarily the most important jobs from your customers’ perspective. They are the most promising jobs from your perspective as a solutions provider. High-value customer jobs are characterized by the following, they are:

  • Important: When customer’s success or failure to get the job done leads to essential gains or extreme pains, respectively. Examples are managing the security risk of an ecommerce website, or designing and implementing the strategy at a company.
  • Tangible: When the pains or gains related to a job can be felt or experienced immediately or often. Examples are traffic during your daily commute, or managing a constantly overflowing email inbox.
  • Unsatisfied: When current value propositions don’t help to relieve pains or create desired gains in a satisfying way. Maybe the desired value proposition doesn’t even exist. Examples are the inexistent cure for hangovers, or calorie-free chocolate.
  • Lucrative: When many people have the job with related pains and gains or when a small number of customers are willing to pay a premium. An example of the former is listening to music on the go. An example of the latter are rare diseases for which customers or insurers are willing to pay a premium.

Here is a list of stakeholders that represent customer segments. But, job title is only one part of creating a customer persona. Here’s what Linkedin Sales Navigator won’t tell you and how to fill the gaps.

If you listen to or watch customers enough, you’ll be surprised at what you’ll discover. Here are some examples.

Don’t send out a questionnaire. Here’s why you need to interview stakeholders to identify their value factors that are most important until you get saturation.

A Act on a selected strategy or solution

L Look back and evaluate

Most businesses fail because 1) they don’t offer the right value proposition-market fit or 2) they don’t have a viable business model. Your business model canvas is anchored on your value proposition. Your value proposition (doing the job the customer wants you to do, removing the pain they have to endure to do it now and offering a product that meets or exceeds customer expectations) starts with understanding your customers. Focusing on your customers or market segments starts with those who touch the problem every day.

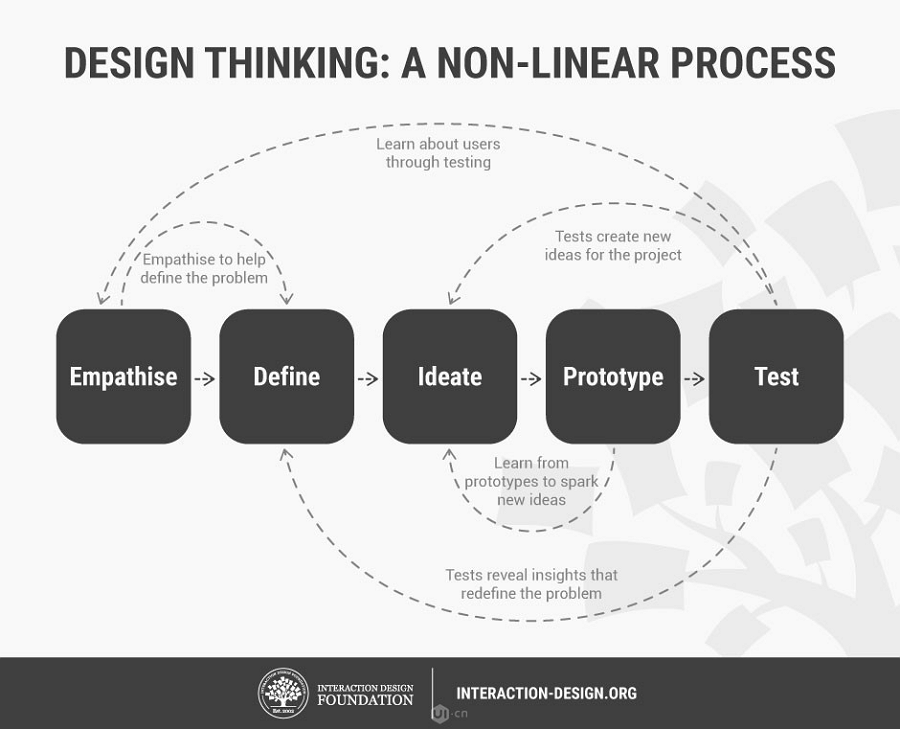
Design thinking describes this process i.e. understanding a problem from the customer perspective, putting yourself in their shoes by either interviewing them, watching them or experiencing what they experience. and create a range of solutions that you then design, prototype and test.

Design Thinking Diagram

Customer centered design means you have to learn how to talk to humans.

Before you do all this, though, decide whether the industry or market you decide to tackle is, the words of my friend, Tom Higley, the CEO at www.101010.net, the right founder-opportunity fit. That usually means finding independence, mastery and purpose and scratching all those psychological itches, be they pathological or not.

Perhaps the most powerful problem is one that you make personal but don’t take personally.

Here’s the problem with saying, “Don’t bring me problems, bring me solutions.”

The education pioneer, John Dewey, said, “a problem well-put is half solved”

That happens when you arm yourself initially with the information you get from being a problem seeker, not a problem solver. Even academic scientists are getting the message.

Image credits: MisterInnovation.com, Interaction Design Foundation

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

The Education Business Model Canvas

Mission Model Canvas

GUEST POST from Arlen Meyers

The business model canvas is one of many useful tools to design, evolve and test products and services business models. While the original model was proposed to help founders create a viable and scaleable business model, it has also helped non-profit executives, as the mission driven business model, and those looking to make a career change, using a personal business model as the Business Model You.
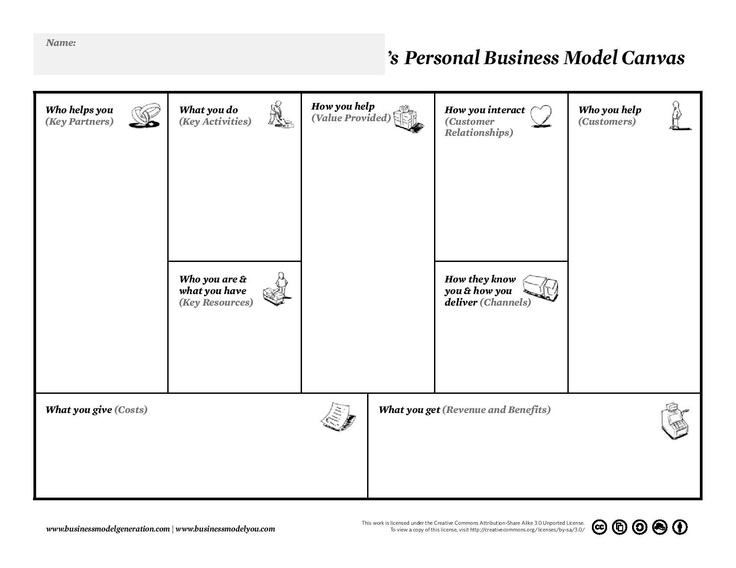
Personal Business Model Canvas

The construct is also useful if you are an edupreneur, trying to create and launch new educational products and services, including new courses, certificates, programs or degree offerings.

Edupreneurship rests on several foundational principles:

  1. Having an entrepreneurial mindset
  2. Intra- and entrepreneurial knowledge, skills, abilities and competencies
  3. Design thinking focused on creating stakeholder and beneficiary defined outcomes
  4. A systems engineering approach to solving wicked problems, like how to fix outcomes disparities and their social determinants
  5. A different business model
  6. More respect for and attention to edupreneurial champions
  7. Better teacher education and training
  8. An incentive and reward system for not just tweaking a failed system , but rather, making it obsolete given the basic structural changes in the US economy
  9. Eliminating unnecessary and burdensome bureaucracy, credentialing that does not add value and administrivia
  10. Paying more attention to and measuring student defined outcomes
  11. Better public-private integration
  12. K-20 integration and alignment

13. Teaching students what they need to win the 4th industrial revolution

14. Embracing cradle to career integration

15. Creating a competent diverse and equitable talent pipeline

We has seen several recent advances in edupreneurship.

Here is the boomer’s guide to teaching millenials.

The UGME steering committee recognizes that medical education programs are faced with the ubiquitous challenge of repeated calls for innovation and that, frequently, these calls do not adequately address the associated resource demands. As medical educators, we have become highly creative in identifying strategies to do more with less, but as we know, this is not a sustainable model of stewardship. In 2016 and 2017, the UGME section collaborated with the Group on Business Affairs (GBA) to explore evolving models to support and sustain UGME programming. A result of this work is the Business Model Canvas for Medical Educators. The original Business Model Canvas was proposed by Alexander Osterwalder in 2008 and has been modified over time to fit other needs. The Table of Contents will direct you to resources, including the Business Model Canvas for Medical Educators template and two examples submitted by institutions who have successfully used the template to secure funding from within their own institution.
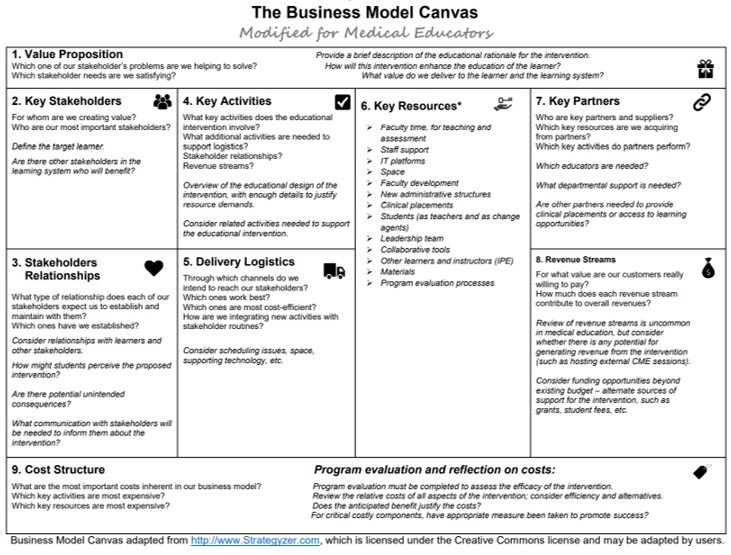
Business Model Canvas for Medical Educators

The edupreneurship business model canvas has a few modifications to the traditional startup one:

Customer segments: The primary customer are students. However, there are many other education stakeholders, including admininstrators, alumni, donors, employers and parents. In addition, for any given subject, potential students will have different backgrounds and experience in the subject, will have different jobs they want done, and, therefore, will have different applications for what they learned, be it finding a job, getting a promotion, or adding value where they presently work.

Value proposition: For each customer segment , you have a specific value proposision. You typically describe it in the course syllabus, telling users about the intended audience, the goals of the course, the learning objectives, and the curriculum. For example, the value proposition for a course I teach to xMBA/HA students is :

This course will introduce graduate level students in healthcare administration and leadership to the principles and practice of healthcare innovation and entrepreneurship defined as the pursuit of opportunity under volatile, uncertain, complex and ambiguous conditions with the goal of creating stakeholder defined value through the deployment of innovation using a valid, automatic, scaleable and time sensitive (VAST) business model.

Following completion of this course, you should be able to:

1. identify gaps in your health entrepreneurship competencies and develop a personal and professional development plan to address them

2. create an organizational culture of innovation, lead innovators and overcome the barriers to healthcare innovation dissemination and implementation

3. identify the multiple clinical and non-clinical ways to practice healthcare entrepreneurship

4. Create a plan to solve a problem inside or outside of your organization that meets the goals of the quintuple aim (Quality, cost, access, experience, waste/business operations)

5. Identify the startup life cycle and challenges at each stage

Channels: This describes how you will deliver your course. Will it be face to face, online or some hybrid model with elements of both?

Customer relationships: This describes how you will get, keep and grow the numbers of students who will take the course, e.g. promoting in the course catalog, attending a career or course proposal day, creating awareness on social media or using word or mouth dissemination from previous students.

Revenue model: This describes how your employer or you will generate revenue from the products. Traditionally, universisty based courses use a “butts in the seats” model, but COVID and new eductional technologies have radically changes the revenue generating possibilities, inluding advertising, freemium models, subscription models and others.

Key resources: This describes the human, physical, intellectual property and financial resources you will need to build, execute and scale your initiative. For example, do you want to copyright your materials, or , do you want to make them an open educational resource using a Creative Commons license?

Key activities: This what you need to do to perform and deliver on your value proposition, like what you will do using a learning management system, like create videos, run office hours, moderate asynchronous virtual discussions and design and grade exams and quizzes

Key partnerships: This describes who can help you, be they guest faculty, educational technology partners, corporate sponsors, e.g. if you are using project based learning techniques or online tools and resouce producers, e.g cases from the Harvard Business School collection.

Costs: This describes the tangible and intangible costs to produce your product. In most instances, your time, opportunity costs and effort will overshadow the monetary costs.

COVID has accelerated the pace of change in higher education, forcing them to create entrepreneurial universities. Teaching faculty how to use the education business model canvas should be part of faculty development to mimimize projecdt and product failure.

Here is what I learned, using the business model canvas, teaching sickcare innovation and entrepreneurship to first year medical students at the University of Colorado.

In this post , Steve Blank offers a new definition of why startups exist: a startup is an organization formed to search for a repeatable and scalable business model.

So is a new course or certificate. Use the education driven business model to make your product desireable, feasible, viable and adaptable and be sure to document your success when it comes time for your evaluation,promotion and tenure review. More likely, though, you will be including it in your failure resume, since, like the vast majority of new products, yours is likely to fail because 1) you offered a product students don’t want to buy or someone does not want to pay for, and 2) you do not have a VAST educational product business model.

Image credits: Strategyzer

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Why So Much Innoflation?

Why So Much Innoflation?

GUEST POST from Arlen Meyers

Inflation is all over the news and at your kitchen table. In case you cut all those economics classes, inflation happens when too much money chases too few goods. It’s happening now because of COVID variations in consumer demand, government stimulus, some fed actions and supply chain glitches. Who knew? The Goldilocks economy describes when prices are not too high, but not too low. Instead, they are just right to stimulate the growth of the economy and the standard of living.

In the midst of all this, we have been seeing a simultaneous rise in sickcare innoflation (i.e. too many overfunded startups and companies creating too few valuable products and services that don’t scale). What’s the answer?

  1. Rethink hospital-based care innovation centers
  2. Create more scalerators and euthanators instead of accelerators
  3. Involve healthcare professionals with the appropriate knowledge, skills, abilities and competencies with an entrepreneurial mindset early in the startup and product development lifecycle.
  4. Change the rules and regulations
  5. Build better ecosystems
  6. Change medical education and training
  7. Fix how we disseminate and implement sickcare solutions and make them equitably accessible.
  8. Close innovation silos
  9. Teach physician entrepreneurs how to play nice with others
  10. Change how we recruit, develop and promote sick care system of system leaders

Building back better will just get us to where we used to be. Instead, we need to create the future better to get us where we want to go. Not too much. Not too little. Just right.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Sickcare Digital Transformation Playbook

Sickcare Digital Transformation Playbook

GUEST POST from Arlen Meyers

First there was the Great Recession. Then came the Great Resignation. Now we are facing the Great Digital Transformation, i.e. how do businesses win the 4th industrial revolution?

When cloud computing collides with 5G, the internet of medical things, quantum computing, virtual reality and virtual medicine, all occuring in an environment of volatility, uncertainty, complexity and ambiguity, things get wicked.

So what should be your next steps if you want to be standing on the middle podium of sickcare digital transformation?

  1. Create value by constantly changing and testing your business models
  2. Scale your culture
  3. Lead innovators, don’t manage innovation systems
  4. Focus on the people part
  5. Transform sick care to healthcare
  6. Fix your dysfunctional processes and eliminate waste
  7. Steal ideas from other industries
  8. Be sure you get the right information and communication tools to the job site
  9. Change your mindset1
  10. Commit to adoption of digital solutions with the same passion that you commit to strategy.
  11. Become an ambidextrous organization
  12. Think big, start small, stay small on projects that matter to end users and patients.

The digital transformation of medicine has become a land grab for investor’s money and end user shelf space. Some think it is a bubble and it remains to be seen how much will be left after the pandemic. One thing you can be sure of, though, is that the solutions will mutate faster than the corona virus and we will need constant innovation to immunize ourselves against obsolescence and the corporate immune system.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

My Advice on Giving Advice

My Advice on Giving Advice

GUEST POST from Arlen Meyers

One way to put a toe in the water of physician entrepreneurship is to become an advisor to a startup founder or client or simply someone who wants your opinion. However, being an advisor that creates value means you have to deliver the 7Ms. You will have to deliver the value that startup CEOs are looking for: money, marketing, making something, management, manpower, mentors, monitoring the environment and mergers and acquisitions.

The same is true if someone asks you to be their mentor. The problem is often that people don’t know how to find a mentor, be a mentor or establish a relationship. The following eight steps can help.

When you get that gig, though, you will have to learn when and how to give advice and how much to give. You also have to deal with founders who have founders syndrome and those who suffer from other entrepreneurial syndromes. In short, many won’t take your advice and you will be left with the feeling that you have wasted your time.

Here’s some advice on giving advice:

  1. When you sign on, clarify expectations about when, how and how often are the best ways to communicate-face to face, email, text or phone, videochat?
  2. Have an agenda focusing on the next critical success factor you need to help achieve. Is it finding money? How about helping to recruit talent to execute the plan and scale?
  3. Avoid having to spend time giving the same advice over and over again by authoring a blog, post or eBook, like this one. Like the flipped classroom, read the assignment and then let’s discuss in class.
  4. If you get ghosted (you haven’t heard from the person who hired you in a while), don’t take it personally. Instead, talk about whether there is a problem, recalibrating your advisory role and whether it should be changed or eliminated.
  5. Use technology to block your time and synchronize schedules
  6. Understand your role as an advisor v a mentor, coach or sponsor. The expectations are different for each.
  7. Don’t work with people you can’t trust, like those who don’t pay you what and when they promised to do so, those who bad mouth you behind your back or those who make you feel unappreciated or ignored or won’t lead when there is inevitable team conflict.
  8. Focus on adding continuous value and delivering results
  9. Assign as much credit for results to others on the team
  10. Here are some tips on how to give advice.

At some point, you have probably noticed that you’re wiser when giving advice to others than you are in making decisions for yourself. You’re not alone. In psychology, it’s called Solomon’s paradox, and it often happens because we have more distance from other people’s problems than our own.

Both the advisee and the advisor have responsibilities so be careful how you pick someone’s brain.

Remember Socrates who said “I cannot teach anybody anything. I can only make them think.” By it’s very nature, advice is just that and can be accepted or ignored. Make it personal, just don’t take it personally when it’s the latter.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.
Sickcare Culture of Conformity versus a Culture of Creativity

Sickcare Culture of Conformity versus a Culture of Creativity

GUEST POST from Arlen Meyers

Sickcare is a culture of conformity and competition. Premeds know it. Medical students and residents learn it. But, once they graduate, they are told they will be paid for value. Unfortunately, few will teach them how to do it and reconcile the culture of conformity and competition with an innovative culture of creativity, collaboration and interprofessional communication.

We should be thankful that we are starting to see some cracks in the armor.

Here are some ways to balance the two mindsets:

  1. Start with higher education reform  To prepare students for a post-Covid future, colleges and universities need to double down on preparing them for digital jobs. But even teaching platform skills aren’t enough. Few employers are interested in hiring candidates who’ve just completed a training program, they’re looking for relevant work experience. The good news is that there are two promising models for colleges to go beyond the traditional career services function to provide students with relevant digital training and work experience.
  2. Overcome the fallacies about creativity. To avoid premature closure, teams should arrive at an “almost final” decision and then intentionally delay action in favor of additional incubation time. During this time, everyone should commit to thinking about the problem and sharing their ideas. If the team can’t find a better approach during the incubation period, they should proceed with their original solution. Leaders can improve group creativity by paying close attention to how ideas are discussed in diverse group settings. They should encourage team members to build on each other’s ideas instead of pushing individual ideas. This doesn’t mean that ideas should be accepted blindly when they contain flaws; instead, they should approach ideas with an open mind to acknowledge useful aspects and improve weaknesses using plussing or the similar “yes, but, and” approach. To promote more creative ideas, leaders should utilize simple tools to capture individual ideas before they are opened to the whole group. Group discussions should be conducted asynchronously, where team members look at each other’s ideas and use them to refine and create new ideas. If done remotely, leaders should find other ways to bring the team together to bond and build trust with each other
  3. Teach creativity and entrepreneurship in medical school and residencies. Here is something so you don’t have to do reinvent the wheel.
  4. Rethink how we recruit and accept medical students Medical education is not alone, as noted in a recent HBR article describing how Goldman Sachs changed how they recruited new hires. Perhaps it is time for medical schools to adopt three new ways of recruiting and accepting medical students.
  5. Give medical students the opportunity to get experience working in a more creative culture as part of an internship or rotation.

6.Train the trainers. Provide faculty with the knowledge, skills, abilties and competencies they need to integrate creativity, innovation and entrepreneurship as part of their basic science and clinical rotations. But, what should an introduction to entrepreneurship teaching and learning include for basic science and clinical faculty who do not have innovation and entrepreneurship domain expertise include?

The learning objective of the module should be to know how to integrate healthcare innovation and entrepreneurship topics into basic science courses and clinical rotations by challenging students with case based, problem based and project based learning in real world settings and applications to help them perfect sickcare entrepreneurial knowledge, skills, attitudes and competencies.

7. Let medical students and residents take a gap year to learn how to create and sell something. Over half of medical schools already have an arrangement whereby students can take a one year leave of absence. But they call it something other than a gap year. They call it getting an MBA. Or, offer them a fellowship in entrepreneurship and innovation.

8. Close the doctor-data scientist digital divide to create a more cooperative culture of data analytics creativity.

9. Hire leaderpreneurs to become department chairs and deans. Rethink the triple threat.

10. Give medical students and residents an exit ramp. The next phase of medical school education reform is in progress. One question medical educators and Deans will have to address is, “What business are we in?” Are you in the business of graduating doctors who will only take care of patients directly, or, are you in the business of creating opportunities for graduates to pursue biomedical careers of their choice, including non-clinical careers that do not involve seeing patients face to face for a significant part of their working life? Patients are not the only stakeholders that have a dog in the sickcare hunt.

11. Teach philanthropreneurship Philanthropreneurship has four elements. First, the driving force must be a passion to make life better for others, especially those who are underprivileged. Second, there has to be an element of giving, whether this is in terms of money or time. Third, there needs to be creativity, the envisioning of novel approaches to solving problems. And finally, philanthropreneurship requires leadership and strategic thinking– directing, organizing, and influencing the efforts of others.

12. Destroy your innovation silos Sick care badly needs innovation if it is to become healthcare . Yet, it’s questionable whether it can be fixed from inside. Despite the popularity of open innovation and community based, participatory innovation networks, healthcare organizations and doctors seem to shun outside ideas and collaboration and are perceived as arrogant know-it-alls, stuck in the ivory tower or healthcare city , when it comes to knowing what’s best for patients. They have a silo mindset that blocks collaboration with other stakeholders in the innovation supply chain. The challenge for most organizations is to create and engage stakeholders.

Innovation starts with mindset. The clinical mindset is different from the entrepreneurial mindset and the ethics of medicine are different from the ethics of business. We need to give experience, educate and train doctors who can reconcile the two. Thankfully, it is starting to happen and it will make better doctors.

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Are doctors wasting their time on entrepreneurship?

Are doctors wasting their time on entrepreneurship?

GUEST POST from Arlen Meyers

Medical students, residents and practitioners around the world are getting more and more interested in entrepreneurship for many reasons. With that, some are questioning the wisdom of doctors bothering themselves with “the business of medicine” , innovation and entrepreneurship given how difficult it is for most doctors to maintain state of the art medical skills, cope with a constantly challenging regulatory environment and keep up with the explosion of medical knowledge. One fundamental question that challenges every doctor is how to reconcile the ethics of medicine with the ethics of business where they practice.

The idea that we are living in an entrepreneurial age, experiencing rapid disruptive technological innovation on a scale amounting to a new “industrial revolution” is a pervasive modern myth. Scholars have written academic papers extolling the coming of the “entrepreneurial economy”. Policymakers and investors have pumped massive amounts of funding into start-up ecosystems and innovation. Business schools, universities and schools have moved entrepreneurship into their core curricula.

The only problem is that the West’s golden entrepreneurial and innovation age is behind it. Since the 1980s entrepreneurship, innovation and, more generally, business dynamics, have been steadily declining—particularly so in the US. As economist Tyler Cowen has found: “These days Americans are less likely to switch jobs, less likely to move around the country, and, on a given day, less likely to go outside the house at all […] the economy is more ossified, more controlled, and growing at lower rates.”

For all the entrepreneurship cheerleading of the last 15 years, the Great Recession accelerated an already alarming decline in new business formation in this country. In the United States, our rates of entrepreneurship have been declining for decades, and those new firms that have been created are employing fewer and fewer people. Meanwhile, techno-oligopolies continue to increase.

After remaining remarkably consistent for decades, the number of new businesses launched in the United States peaked in 2006 and then began a precipitous decline – a decline accelerated by the Great Recession. From 2002 to 2006, the economy produced an average of 524,000 new employer firms each year. Since 2009, however, the number of new business launched annually has dropped to about 400,000, meaning the United States currently faces a startup deficit of 100,000 new firms every year – and a million missing startups since 2009.

COVID has had a significant impact on entrepreneurship. Here is another take on the effect of COVID on entrepreneurship. But, entrepreneurship by necessity has its dark side.

Research suggests that over the past two decades, the number of high-value startups has declined, sparking significant debate over what’s causing the drop, how to fix it, and whether or not it’s a problem that needs fixing. Here are six reasons why that might be true:

  • Theory 1: Entrepreneurs are motivated more by the lifestyle than by viable business ideas
  • Theory 2: Tougher regulation is hurting high-growth companies
  • Theory 3: Big businesses have changed the way they operate
  • Theory 4: Entrepreneurs lack the right training
  • Theory 5: The gig economy is affecting would-be entrepreneurs’ experience
  • Theory 6: The problem is a measurement issue

Here is the tale of the tape:

  • In 1980, 15% of all U.S. firms had been created the year before. In 2011, that share had been halved, according to census data.
  • In 1997, for the first time in this country’s history, more Americans worked at companies with 250 or more employees. The gap has steadily grown since, aside from a notable blip in the early 2000s. The biggest single percentage increase was between 2007 and 2008, as the Great Recession took hold.
  • Three-quarters of U.S. incorporations that we do have issue no payroll, mostly for the self-employed.
  • Though our outsized venture capital market means we have a high share of iconic, rocket-ship growth companies, the United States is lagging other rich country peers in the crucial middle category: new, growing, innovative companies trying to bring efficiencies to industries that may last.

Part of the problem derives from some misconceptions and differences in our interpretations of physician entrepreneurship:

  1. Each doctor has his or her definition of physician entrepreneurship, value and innovation
  2. Physician entrepreneurs play many different roles creating user defined value
  3. Those roles depend on whether they are medical practice entrepreneurs, social entrepreneurs, technopreneurs, intrapreneurs, educational entrepreneurs, physician service providers or investors
  4. Innovation ecosystems vary from one domain e.g. digital health to another, like biopharma
  5. There are vast international cultural, social and political systems differences that help or hinder physician entrepreneurship.
  6. Rules drive ecosystems. Rules variation around the world often reflects the values of a given citizenry at a given point in time. While health system problems are universal (cost, access, quality, changing demographics, supply, demand, equity), the solutions vary tremendously.
  7. Creating value and wealth is but one step. Sharing the wealth that results, justice and equity are separate issues that can either raise the overall standard of a health system in a given country or drive another wedge between the haves and have nots. It also determines how physician entrepreneurs are perceived as either ruthless, greedy profiteers or instruments of social justice and improvement.
  8. The gaps between how younger generations and older rulers see the world are widening (e.g China and somewhat reflected by Sanders supporters in the US elections) The “dream” constantly evolves from financial security to higher levels of needs like democracy, international connectedness and security and a better life for families and children.
  9. Regardless of which way physicians choose to pursue entrepreneurship, it takes teamwork and the involvement of many different participants with varying skill sets. Each contributes something different.
  10. Biomedical entrepreneurship is a marathon relay race. As such, any team is only as strong as its weakest link.
  11. Few health professionals have an entrepreneurial mindset, in large part because of how they are chosen and the lack of bioentrepreneurial education and training in their programs.
  12. Politics, ego and greed get in the way of substantive change in the US sickcare system of systems.

Judging by the headlines on their LinkedIn profile, more and more MD/DOs are innovators, entrepreneurs and non-clinical consultants. Many are starting or working with biomedical and clinical startups, including a group of medical school graduates who don’t do a residency. But:

  1. They are not trained to do so
  2. Entrepreneurship in the US has been in a downward spiral in the US for the past 40 years.
  3. Most startups will fail
  4. Most startups don’t have money to pay people
  5. There is an innovation bubble.
  6. Job security is low
  7. You have to deal with people who have entrepreneurial psychopathologies are simply untrustworthy.
  8. Students loan burdens are rising
  9. Many are not in it for the long run
  10. There are unrealistic expectations on both the consultant/employee and employer side.
  11. Most MD/MBA programs should be terminated
  12. Innovation theater is pervasive.

If you thought getting a side gig or pursuing a non-clinical career was Plan B but now realize the grass really isn’t that much greener, maybe it’s time for Plan C.

The underlying assumption behind creating incentives for early involvement of physicians in entrepreneurship is that it will improve outcomes and company success. However, we lack the data that validates that assumption.

Doctors are wasting their time typing into EMRs, complying with administrivia, being on hold to get prior authorization, and answering unnecessary phone calls from patients that could be avoided with proper engagement and education. If anything, they are not spending enough time creating user defined value through the deployment of innovation.

At its core, though, we need to change the rules about measuring quality, clearing products, paying to things, providing equitable access and insurance coverage, and eliminating waste and administrivia cost, and narrowing inequitable value sharing. Otherwise, we are just parading shiny new objects.

We need to fix sickcare USA before we decide how or whether we change how we fund it. Otherwise, we will be just wasting more and more money.

We need to do a better job of measuring the input, output and impact of physician entrepreneurship including not just creating new companies, but interventions in medical practice entrepreneurship, social entrepreneurship, intrapreneurship, edupreneurship and other non-commercial roles as well.

International biomedical entrepreneurship will continue to grow With that, however, will be more challenges to use the results to make patients, systems and societies better. By doing good, physician entrepreneurs can do well, but there are formidable headwinds preventing them from doing so. Unless we have evidence to the contrary, the null hypothesis is physician entrepreneurship is a waste and , in retrospect, just sounded like a good idea at the time. I hope the results prove me wrong.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Teaching to Win the 4th Industrial Revolution

Teaching to Win the 4th Industrial Revolution

GUEST POST from Arlen Meyers

The Coronapocalypse is forcing us to rethink who, how and what we teach. Regardless of how we do it, college students don’t learn much and the teacher experience is eroding.

Many not for profits are directing their efforts to provide equitable access to public education. However, putting more students in a broken, dysfunctional system won’t yield the outcomes and impact we want. Instead, the very structure and process of education will need to change if we are to provide students with the knowledge, skills, abilities and competencies they need for jobs that have yet to be created.

What’s more, unless we address the gender social and cultural stereotypes, the 4IR could make gender inequity worse, not better.

Companies like Infosys still hire lots of engineers. But today, Ravi Kumar, the Infosys president, is not looking just for “problem solvers,’’ he says, but “problem-finders,’’ people with diverse interests — art, literature, science, anthropology — who can identify things that people want before people even know they want them.

If for nothing else than the future of your children, take 12 minutes to watch this:

If you agree, then thriving in the 4th industrial revolution will require nothing short of restructuring public education at all levels, not just k-12. Even doctors will need to change how they educate their young. How many things can you do with a paperclip?

One goal should be to create entrepreneurial schools and universities, and by that I don’t mean teaching children how to start businesses. Instead, creating the entrepreneurial mindset is about the pursuit of opportunity with scarce resources with the goal of creating user defined value through the deployment of innovation. Creating a successful business in but one of many ways to do that.

Here are 10 different ways to encourage youth entrepreneurship. The same techniques might apply to graduate students as well.

Other learning objectives and curriculum themes are emerging:

  1. Encouraging private, public and academic collaboration to define market based competencies
  2. Teaching horizontally, not vertically, in limiting smokestack domains
  3. Developing soft skills that are in high demand
  4. Experience cultural competence, diversity and inclusion
  5. Alternative pathways for teacher training and development
  6. Job searching techniques that are state of the art
  7. Mandatory experiential learning opportunities
  8. Developing and testing alternative intelligence measures
  9. Replacing memorization with creative problem solving, problem seeking and divergent thinking.
  10. Hiring for creativity and finding and supporting educational reform champions
  11. Like sick care, recognizing and addressing the socioeconomic determinants of academic failure, like housing, illness, disability and nutrition.
  12. Rehabilitating the brand image of teachers
  13. Teaching STEAMpathIE and rethink STEM as BMETALS
  14. Preparing students for the jobs of the future that have not yet been created.
  15. Teach them how to work in and manage virtual international teams.

Here’s another short list:

  1. public speaking
  2.  writing well
  3. storytelling (see 1-2)
  4. critical thinking (not cynicism)
  5. good manners
  6. active listening (hear with your eyes)
  7. networking (trust and giving)
  8. good customer service
  9. how to sell
  10. to fight against entitlement

Curriculum redesign for medical students and residents will need to include:

  1. Data literacy
  2. Interprofessional bioentrepreneurship
  3. Digital health policies and practice
  4. Care coordination between the medical team and the patient care circle
  5. Cost-effectiveness analysis
  6. The pharmaceutical value chain and drug pricing
  7. Customer service
  8. Ethics and professionalism
  9. Personal financial literacy and planning
  10. Nutrition

Here is how automation will affect economies around the world.

Here are some recommendations to Promote digital education and workforce development

“As AI applications accelerate across many sectors, it is vital that we reimagine our educational institutions for a world where AI will be ubiquitous and students need a different kind of training than they currently receive. Right now, many students do not receive instruction in the kinds of skills that will be needed in an AI-dominated landscape. For example, there currently are shortages of data scientists, computer scientists, engineers, coders, and platform developers. These are skills that are in short supply; unless our educational system generates more people with these capabilities, it will limit AI development.”

Our economy and standard of living hinges on meeting these wicked challenges. But, like medicine, government and other risk-averse and sclerotic industries, the resistance to change will be substantial. Only bottom-up pressure led by creative, courageous innovators who teach what they practice, in collaboration with non-profits and government agencies, will remove the obstacles in our path. Many of those obstacles are in the classroom next door or the corner office or the halls of government.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Advances in the Management of Worthless Meeting Syndrome

Advances the management of worthless meeting syndrome

GUEST POST from Arlen Meyers

Now that we have all been stuck inside for almost two years, many of us are suffering from an exacerbation of worthless meeting syndrome (WMS) , most recently remotely.

Of course, worthless meeting syndrome is a well-described chronic disease which has periodic exacerbations. It can be endemic or global with recovery and remissions. Here are the signs and symptoms.

One meeting expert notes that bad meetings are the bane of the corporate world — and yet despite what appears to be an overwhelming consensus that they’re often unnecessary and unproductive, many workplaces continue to struggle to avoid them. In this piece, the authors discuss the psychological pitfalls that lead us to schedule and attend too many meetings, and share strategies to help employees, managers, and organizations overcome those challenges. While there’s no way to completely eliminate the universal human biases that drive these tendencies, a greater awareness of the psychological factors at play can help us all work towards healthier communication norms, more-effective interactions, and cleaner calendars.

My recommended treatment is to refuse to attend any meetings:

  1. Where there is no agenda
  2. Where it is informational that could be communicated some other way
  3. Where we discuss what we discussed last time without taking action
  4. Where my input is required to inform a decision or take action on something
  5. Where there is no psychological safety
  6. Where a working group could have done the grunt work offline and reported their findings for approval or modification
  7. On weekends or nights unless absolutely required due to mission critical time zone issues or deadlines
  8. The meeting last longer than 45 min, if not 30
  9. No one takes minutes and there are action items for next (if necessary) meeting
  10. There are more than 7 people in the meeting
  11. Lobby your congressional delegation to make them illegal As remote work becomes more widespread, the parliament of Portugal recently passed a law banning bosses from contacting employees after working hours by phone, message or email. Violations of the new law — designed to “respect the privacy of the worker,” including rest and family time — could result in fines. Employees there have also been given the right to opt out of remote work, and to be reimbursed for expenses incurred while working from home.

Note: Ivermectin has not been shown to be clinically effective.

If your boss insists that you attend and you are accused of not being a team player, then get a note from your doctor. They are available online at www.wms.com

For the meeting junkie who has everything, we are also offering a clock at our WMS store that not only measures the length of the meeting, but also the prorated amount of money you are paying for the people to attend the meeting, similar to the US National Debt clock.

Image credit: BringTIM.com

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.