Author Archives: Arlen Meyers

About Arlen Meyers

Arlen Meyers, MD, MBA is an emeritus professor at the University of Colorado School of Medicine, an instructor at the University of Colorado-Denver Business School and cofounding President and CEO of the Society of Physician Entrepreneurs at www.sopenet.org. Follow along onSubstack.

Happy Brains Make Happy Doctors

Happy Brains Make Happy Doctors

GUEST POST from Arlen Meyers

In this day and age, many doctors have fallen into a negative rut. They are filled with cynicism, negativity, complaining and self-defeating thoughts, many of which we see posted on social media sites like LinkedIn groups and Twitter feeds.

One of your entrepreneurial habits should be to be positive. To be positive, you need to practice having positive thoughts.

Michelle Gielan’s Resilient Optimism is a science‑backed guide showing that optimism is not a fixed trait but a trainable skill, built through five core behaviors that help people stay hopeful, grounded, and effective in challenging times.

The book structures its advice around five repeatable habits:

Recalibrate your mindset – Shift focus from setbacks to what’s working, reframing negative thoughts.

Transform your stress response – Reframe pressure as a performance‑fueling resource rather than a drain.

Triage your commitments – Protect time, energy, and attention by prioritizing what matters most.

Recharge strategically – Use recovery methods that truly restore capacity, avoiding burnout.

Connect the dots – Notice and share evidence of progress and the impact of your actions.

I would add learning how to say “no”.

Having negative thoughts has a neuropsychological basis, so re-wiring will take some cortical renovation that takes practice, practice, practice.

Here are the steps to having a happy brain:

1. Start noticing when you have negative thoughts

2. Some of your negative thoughts might, in fact, have a factual basis. However, in many or most instances, they won’t, so find evidence to the contrary.

3. With practice, practice, practice you should be thinking positively in 4 months. Imagine. Happy by this Fall.

4. Step outside of yourself

5. Exaggerate the absurdity of your negative thoughts. Can you tell a joke about your negative self? Here’s one for a start:

A woman was at her hairdresser’s getting her hair styled for a trip to Rome with her husband. She mentioned the trip to the hairdresser, who responded:

“Rome? Why would anyone want to go there? It’s crowded and dirty. You’re crazy to go to Rome So, how are you getting there?”

“We’re taking American”, was the reply. “We got a great rate!”

“American?” exclaimed the hairdresser.” That’s a terrible airline. Their planes are old, their flight attendants are ugly, and they’re always late. So, where are you staying in Rome?”

“We’ll be at this exclusive little place over on Rome’s Tiber River called Teste.”

“Don’t go any further. I know that place. Everybody thinks it’s going to be something special and exclusive, but it’s really a dump, the worst hotel in the city! The rooms are small, the service is surly, and they’re overpriced. So, whatcha’ doing when you get there?”

“We’re going to go to see the Vatican and we hope to see the Pope.”

“That’s rich,” laughed the hairdresser. “You and a million other people trying to see him. He’ll look the size of an ant. Boy, good luck on this lousy trip of yours. You’re going to need it.”

A month later, the woman again came in for a hairdo. The hairdresser asked her about her trip to Rome.

“It was wonderful,” explained the woman, “not only were we on time in one of American’s brand-new planes, but it was overbooked, and they bumped us up to first class. The food and wine were wonderful, and I had a handsome 28-year-old steward who waited on me hand and foot.

And the hotel was great! They’d just finished a $5 million remodeling job, and now it’s a jewel, the finest hotel in the city. They, too, were overbooked, so they apologized and gave us their owner’s suite at no extra charge!”

“Well,” muttered the hairdresser, “that’s all well and good, but I know you didn’t get to see the Pope.”

“Actually, we were quite lucky, because as we toured the Vatican, a Swiss Guard tapped me on the shoulder and explained that the Pope likes to meet some of the visitors, and if I’d be so kind as to step into his private room and wait, the Pope would personally greet me. Sure enough, five minutes later, the Pope walked through the door and shook my hand! I knelt down and he spoke a few words to me.”

“Oh, really! What’d he say?”

“He said: “Where’d you get the awful hairdo?”

6. Have a positive thought in reserve when it is time to change lanes.

Now that Microsoft owns LinkedIn, maybe they will begin to offer an option where group managers can ask them to flag negative posts as a form of social cognitive reappraisal. Wouldn’t that be a positive step?

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Changing Minds to Mindsets

Changing Minds to Mindsets

GUEST POST from Arlen Meyers

Fostering bioimedical and clinical innovation will mean creating entrepreneurial universities with academic entities, like medical schools, that have entrepreneurial faculty that graduate all students with an entrepreneurial mindset.

There are 6 characteristics of the entrepreneurial mindset.

1. Personal growth relates to the size of the challenge, not the size of the kingdom. What motivates real innovators is the more exciting challenge, not the number of people reporting to them. The “size of the difference” they will make is more inspiring than the “size of the business.” They relish getting out of their comfort zone, and into the unknown.

2. The new direction is the challenge, not the destination. The challenge is the transformation vehicle for true innovators, and not a performance goal. They focus on legacy creation, not legacy protection. They ignore failures and are constantly looking at the progress made. They treat innovations reviews like performance reviews.

3. Be an attacker of forces holding people back, not a defender. Real innovators start by questioning the world order rather than conforming to it. They begin by confronting the forces holding everyone back, rather than living with it. The forces include mindset gravity, organization gravity, industry gravity, country gravity, and cultural gravity.

4. New insights come from a quest for questions, not a quest for answers. This discovery mindset searching for new questions drives real innovators away from more of the same. They fundamentally become value seekers; they look for value in every experience, in every conversation. They don’t seek prescriptions, they seek possibilities.

5. Stakeholders must be connected into the new reality, not convinced. True innovators tip stakeholders into adopting and even co-owning the orbit-shifting idea. They go about tipping the heart first, assuming the mind will follow. They seek smart people, who openly express their doubts, and then collaborate to overcome them.

6. Work from the challenge backward, rather than capability forward. Overcoming execution obstacles is combating dilution, not compromising, for these innovators. Their mindset is not “if-then” but “how and how else?” They convert problems to opportunities, and often the original idea grows far bigger than the starting promise

Training minds is easier than changing them. Changing mindsets is even more difficult than changing minds.

– A new survey by the Center for Connected Medicine (CCM) at UPMC reveals that artificial intelligence (AI) continues to be a top priority for senior leaders in the healthcare industry.

– For the second year in a row, executives cited AI as both the most exciting technology and the most improved, highlighting its potential to transform healthcare.

But top of mind is not top of mindset.

Here are some ways to future proof your mindset.

Both students and faculties need to be more proactive than reactive to opportunities and they need administrators and leaders to provide them with the innovation systems and infrastructure they need to thrive.

Too much of academe is about features, not benefits, problem solving, not problem seeking, spoon feeding, not challenging learners to figure out how to feed themselves.

Image Credit: Gemini

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Time to Rethink Pitch Fests and Business Plan Competitions

Time to Rethink Pitch Fests and Business Plan Competitions

GUEST POST from Arlen Meyers

Pitch fests happen almost every week somewhere in the US, They happen in primary schools, high schools, institutions of higher learning , incubators and accelerators. In addition, the spring and the fall are B school business plan competition season, so look for tweets about who won and pictures of those smiling millennial faces holding big cardboard checks.

These competitions serve many purposes, but, fundamentally the objective is 1) to practice your presentation skils, 2) to get feedback, 3) to find money

I have participated on both sides of the check, as both pitcher and catcher (judge) and have always found the format wanting.

Carl Schramm describes the problem:

 If you look at all our older major corporations — U.S. Steel, General Electric, IBM, American Airlines — and then you look at our newer companies like Amazon, Apple, Facebook, Microsoft, none of these companies ever had a business plan before they got started. Empirically, it appears as if you don’t need a business plan.

Second, the business planning process is largely generated as a preview for venture capital. As I show in my book, from empirical studies, much less than 1% of all new startups ever see a venture capitalist. Much less than 1% of all new companies every year have venture backing of any kind. So, I largely view the creation of a business plan as something of a waste of time.

The third problem is that it seems to make starting a business somewhat like a cookbook. If you do this, and then you do this, and then you do this, the cake will come out okay. And that’s really not how it happens.

I think it is time to rethink these events, and, it seems, so do some investors who are moving towards data-driven investing.

EQT Ventures in Europe takes data-driven investing to a new extreme. The 2-year-old VC firm, which is part of private equity group EQT, uses an AI-driven data platform called Motherbrain to help it make investment decisions. The firm’s €566 million fund backs companies at all stages—except seed—with €3 million to €75 million checks. So far, the firm has invested in 22 startups.

Analytics partner and former VP of analytics at Spotify, Henrik Landgren, said Motherbrain could’ve identified Spotify and Uber as unicorns in the companies’ early days. He believes letting software play a key role in crafting one’s portfolio is “the next evolution of VC.”

Conditional on getting to the stage of submitting a business plan, the judges’ scores have almost no predictive power in determining which entrepreneurs will succeed.

1. The whole notion of writing a business plan v a business model canvas has been called into question given the reality that no battle plan survives the first shot. A colleague suggested “Wild Ass Guess” competition as another way to brand them.

2. Pitches should be limited to no more than m5inutes. Who, in this day and age, watches anything for more than 3 minutes before moving to the next You Tube? Like the hangman’s noose, it focuses the mind. Taking it one step further, idea pitches should last no more than 1 minute.

3. The award money has to be spent on the business, not be used to finance a trip to Europe this summer

4. Winners must commit to passing it forward. There should be an expectation that they will contribute money, effort, time , mentorship or other things to future events and applicants

 5. We should publish rates of startups, success rates, exits and the contributions made to the local, regional and national economy

6. We should require that applicants participate in a pre-submission bootcamp to get their presentations ready for prime time in an effort to not waste the time of volunteers who were hesitant to help in the first place. Here are the skills we want participants to practice:

  1. The professionalism of the technical parts and the presentation itself
  2. Was the presentation appropriate for the audience?
  3. Did you talk about the why or the how of your idea and why did you choose to do that?
  4. Did you tell a story and did it have a biginning, a middle and an end with heros and villains?
  5. Could someone with a fifth grade reading level understand it?
  6. Did you props and other media?
  7. Did you end with a strong call to action?
  8. Did you pitch to the heart or the head of your audience
  9. Did this look like your first rodeo or did you practice?
  10. Was your presentation scripted, look like you “winged it” or did you appear more confident and relaxed?

7. Spend most of the time in front of judges “defending their thesis”. They should be required to think on their feet, answering “what ifs” , since that’s what they will have to do the moment they walk out of the award ceremony.

8. Awardees should be required to participate in iTeams to develop and further test and validate their ideas. They should be encourged to resubmit their business ideas in Phase 2 to apply for money to scale their validated models, similar to the SBIR process. Call it the Scalerator Competition.

9. Awardees must agree to submit testimonials, what the Disney Corporation calls Magical Moments, telling their stories not just about success, but how they overcame adversity and failure.

10. Awardees should spend some time in a real startup, perhaps with the sponsors who put up the bucks to help pay for the event, as an experiential learning opportunity

11. The winner take all format leads to churn and discourages further participation by those who are not the winners

12. Judges come with biases they apply to their decisions whether they use instinct or analysis. There are many false negatives (passing on ideas that are eventually successful) and false positives (getting on ultimate failures).Since we don’t really track long term outcomes of these events, we don’t know many there are.

13. Picking one winner or loser is different than picking a number of companies as part of a risk portfolio. Picking winners in a calm market is something first-timers do just as well as old hands, but avoiding losers is where skill and experience matters.

14. Customers are the ultimate arbiters of success or failure. Rewards should go those teams who have demonstrated they have created them.

15. Here’s another way to launch entrepreneurs and their ideas.

Another issue is the lack of consistency, criteria and implicit bias judging business plans. Business plan judging software has made things more consistent, but as long as humans are applying subjective criteria, there will be some variation. For example, here are some do’s and don’ts from one HBS judge.

Business plan competitions , to some, are a waste of time. Instead, maybe we should have Business Model or just idea competitions.

Encouraging students to submit pie in the sky plans that have little or no validity, judging them using vague and unproven methodologies, awarding them money that they don’t even have to spend on their business ideas and cutting them loose afterwards means the biggest winner is the B school building brand equity. For doctors, scientists and engineers, pressing them to write a business plan before using a validation method is like writing a scientific paper and then doing experiments to find the data you used to justify the conclusions.

Can you imagine pitching at a Quantum Business Plan competition?

We need to stop reality TV B school business plan competitions and pitch fest reward structures and get real about business model and idea competitions.

Image Credit: Pexels

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Trends in Medical School Innovation and Entrepreneurship Education

Trends in Medical School Innovation and Entrepreneurship Education

GUEST POST from Arlen Meyers, M.D.

Biomedical and health entrepreneurship continues to expand around the world. Driven by global pressures to optimize the allocation of scarce resources, life science bioentrepreneurs are creating innovative products, platforms, service and systems that deliver more value. As a result, the demand for biomedical and health professional entrepreneurial talent has increased and biomedical and health innovation and entrepreneurship education and training (BEET) programs are growing to fill the gap.

Authors of a 2019 analysis of 171 allopathic medical schools conducted an exhaustive search of the published literature and websites of existing medical school innovation and entrepreneurship (MS I&E) programs, with an emphasis on answering the following three questions:

1. How are I&E programs organized and integrated with the medical school curriculum?
2. What are the core competencies of the I&E program?
3. How are the core competencies measured/evaluated?

Twenty-eight I&E-oriented medical education programs were identified from 26 schools; all of the programs integrated faculty leadership with backgrounds in medicine, engineering, and/or business/entrepreneurship. Of the programs, 57% (16/28) had been launched within the past four years and 75% (21/28) based program enrollment on a selective application process. Nearly all (27/28) incorporated lecture series and/or hands-on modules as a teaching technique. The most prevalent metric was completion of a capstone project (22/28; 79%). At least 15.2% (26/171) of American and Canadian allopathic medical schools include the option for students to participate in an I&E curriculum-based program.

In a few short years, educational offerings in MS I&E have accelerated, in part due to the impact of the COVID pandemic. Trends include:

  1. Sharing lessons learned teaching medical students innovation and entrepreneurship
  2. Experimenting with various program business models
  3. Creating medical student entrepreneurs
  4. Rethinking MS I&E
  5. Designing a curriculum map and defining learning objectives, entrustable professional activities and knowledge,skills, abilities and competencies
  6. Mentoring and guiding medical students
  7. Offering non-clinical-career options
  8. Providing exit ramps
  9. Rethinking how we select medical students
  10. Resetting the future of academic medical center work
  11. Using principles of medical education reform and what we should be teaching in MedEd 2030
  12. Training MS I&E faculty
  13. Encouraging interprofessional and transdisciplinary entrepreneurship programs
  14. Integrating premed, medical student and postgraduate programs
  15. Encouraging life-long learning

We should teach innovation, entrepreneurship and the business of medicine in medical schools, not MD/MBA programs. MBE programs are a better option for those interested in getting an idea to a patient.

Here are the many reasons why physician entrepreneurship is important and why we are likely to see more of the international design, development and deployment of MS I&E programs in both allopathic and osteopathic schools as well as other health professional schools, including nursing, pharmacy and public health schools. Ultimately, as a result, patients and sickcare systems will be the beneficiaries and doctors will be better and happier.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.
Why We Need Digital Health Package Inserts

Why We Need Digital Health Package Inserts

GUEST POST from Arlen Meyers, M.D.

The Food and Drug Administration announced new rules for nutrition labels that can go on the front of food packages to indicate that they are “healthy.”

According to one source, a package insert is a document included in the package of a medication that provides information about that drug and its use. For prescription medications, the insert is technical, and provides information for medical professionals about how to prescribe the drug. Package inserts for prescription drugs often include a separate document called a “patient package insert” with information written in plain language intended for the end-user — the person who will take the drug or give the drug to another person, for example a minor. Inserts for over-the-counter medications are also written plainly.

In the US the document is called “prescribing information” or the “package insert” (PI) and layperson’s document is called the patient package insert (PPI). In Europe the technical document is called the “summary of product characteristics” (SmPC) and the document for end-users is called the “patient information leaflet” (PIL) or “package leaflet”.

Given the confusion about 1) which digital health product to prescribe for any given patient, 2) the fact that many products are actually consumer products designated to provide information and education, not diagnosis or treatment, and 3) most are not clinically validated or cost-effective, perhaps it’s time to require package inserts for the prescriber and the patients.

Prescription digital therapeutics is also being added to the therapeutic armementarium and is raising several questions about safety, effectiveness, cost-effectiveness, ROI, reimbursement and regulatory requirements, including whether package inserts should be required, how they should be made available to patients, and what they should include.

What is in a package insert is described and required by the FDA and includes:

  • Clinical pharmacology – tells how the medicine works in the body, how it is absorbed and eliminated, and what its effects are likely to be at various concentrations. May also contain results of various clinical trials (studies) and/or explanations of the medication’s effect on various populations (e.g. children, women, etc.).
  • Indications and usage – uses (indications) for which the drug has been FDA-approved (e.g. migraines, seizures, high blood pressure). Physicians legally can and often do prescribe medicines for purposes not listed in this section (so-called “off-label uses”).
  • Contraindications – lists situations in which the medication should not be used, for example in patients with other medical conditions such as kidney problems or allergies
  • Warnings – covers possible serious side effects that may occur
  • Precautions – explains how to use the medication safely including physical impairments and drug interactions; for example “Do not drink alcohol while taking this medication” or “Do not take this medication if you are currently taking MAOI inhibitors“
  • Adverse reactions – lists all side effects observed in all studies of the drug (as opposed to just the dangerous side effects which are separately listed in “Warnings” section)
  • Drug abuse and dependence – provides information regarding whether prolonged use of the medication can cause physical dependence (only included if applicable)
  • Overdosage – gives the results of an overdose and provides recommended action in such cases
  • Dosage and administration – gives recommended dosage(s); may list more than one for different conditions or different patients (e.g., lower dosages for children)
  • How supplied – explains in detail the physical characteristics of the medication including color, shape, markings, etc., and storage information (e.g., “Store between 68 and 78°F “)

Of course, there would need to be some modifications, like:

  1. Safety and efficacy
  2. Cybersecurity risks
  3. Data security
  4. Data , privacy, ownership and transfer rights
  5. Side effects
  6. Designation as a consumer product or a diagnostic or therapeutic device
  7. Generic substitution possibilities
  8. Adverse app reactions
  9. App-app interactions
  10. Compatibility with other drugs or devices

One thing that will not be in the insert will be what all this costs to you or someone else who has to pay for it.

Research shows that “Safety of apps is an emerging public health issue. The available evidence shows that apps pose clinical risks to consumers. Involvement of consumers, regulators, and healthcare professionals in development and testing can improve quality. Additionally, mandatory reporting of safety concerns is needed to improve outcomes.”

It is short-sighted, however, to let DTC medical apps slip under the regulatory radar. As described in a recent article for Nature, they could turn out to have costs which insurers or taxpayers might ultimately be responsible for.

But, the FDA is not the only agency with regulatory power. How about the Federal Trade Commission? Almost every promotion these days claims “AI-powered” What should be the truth in advertising standards to make that claim? Should there be something like a nutrition label ?

Medical student and resident education in clinical informatics, including artificial intelligence, is a good start. Here are some potential curricular and extracurricular learning opportunities for artificial intelligence in medicine.

At this point you are probably thinking, “We have enough regulations and we love our APPs. So what if they don’t make us any better.”

Go shove your insert.

Next, you’ll be telling us it has to have all that cotton in the bottle too.

Image Credits:

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Should a Bad Grade in Organic Chemistry be a Doctor Killer?

NYU Professor Fired for Giving Students Bad Grades

Should a Bad Grade in Organic Chemistry be a Doctor Killer?

GUEST POST from Arlen Meyers, M.D.

A recent article described the termination of an NYU organic chemistry professor in response to a student petition. When the professor pushed students’ grades down, noting the egregious misconduct, he said they protested that “they were not given grades that would allow them to get into medical school.” The reporter noted that, in short, this one unhappy chemistry class could be a case study of the pressures on higher education as it tries to handle its Gen-Z student body. Should universities ease pressure on students, many of whom are still coping with the pandemic’s effects on their mental health and schooling? How should universities respond to the increasing number of complaints by students against professors? Do students have too much power over contract faculty members, who do not have the protections of tenure?

And how hard should organic chemistry be anyway? One faculty member said, “Unless you appreciate these transformations at the molecular level, I don’t think you can be a good physician, and I don’t want you treating patients.”

I know the feeling. While organic chemistry is termed a “doctor killer” by premedical students, getting any grade less than an “A”, typically in science, technology, engineering, or math subjects, can doom your application. When I saw that B I got in physics in my junior year of college, I started thinking about Plan B. Then I really learned the gravity of the situation.

Despite the noise and groaning, medical school applications continue to rise, driven by many factors. However, the medical school education model dates back to the Flexner report issued in 1910. Many are trying to address the challenges of how to train the biomedical research and practice workforce to win the 4th industrial revolution, but progress has been slow. Here were the challenges facing medical schools in 2015. Things have not radically changed. Medical educators, particularly those in public medical schools, will continue to face several basic problems in the coming years. The “invisible enemy” has exacerbated many.

We should rethink how we recruit and accept medical students.

Here are some questions that should inform that transition:

1. Do doctors really need to be that “smart”? GPAs can vary significantly across different medical schools, so it pays to do your research before applying. The Association of American Medical Colleges (AAMC) reported an average GPA for medical school of 3.60 across all applicants for the 2021-2022 application cycle. For the same year, applicants had an average science GPA of 3.49 and an average non-science GPA of 3.74.

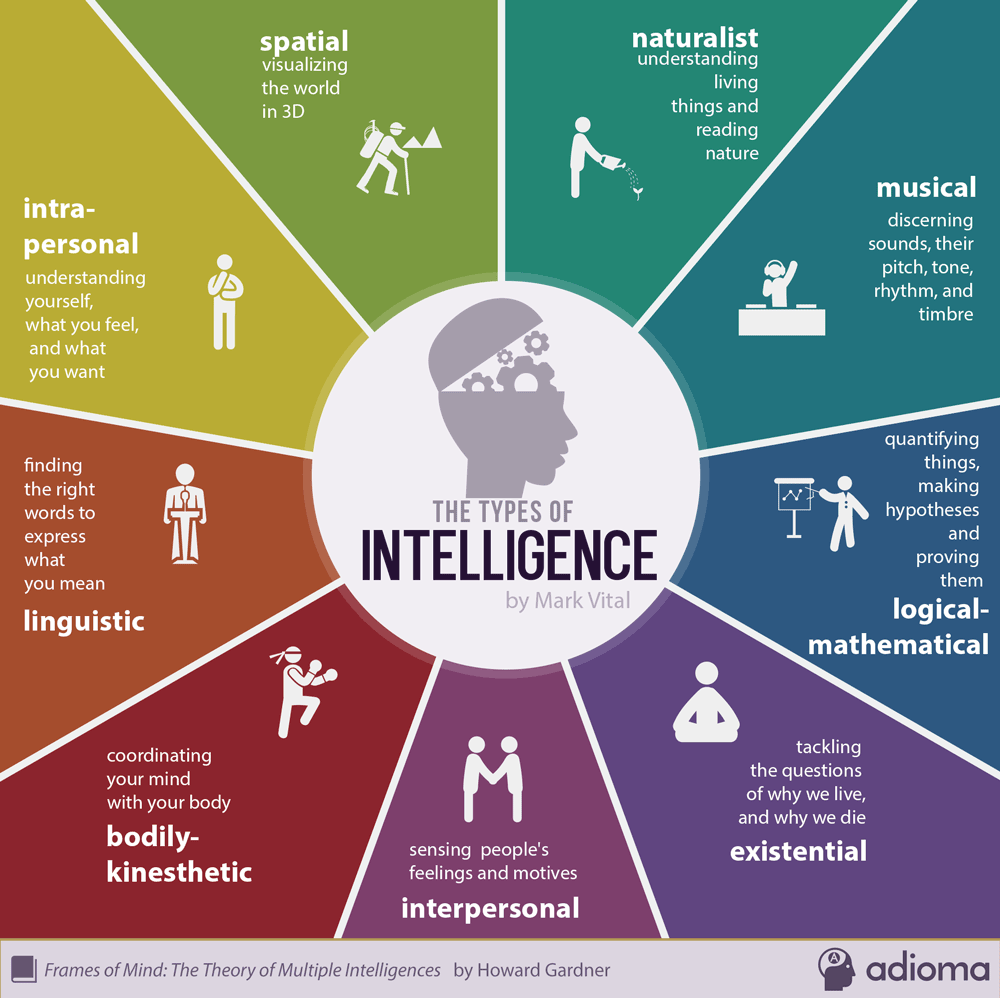
2. What kind of intelligence do doctors need to meet the needs of their stakeholders and communities?

Types of Intelligence by Mark Vital

3. Do patients really care what grade their doctor got in organic chemistry, or, for that matter, whether they graduated last in their class from medical school?

4. How has the pandemic and the persona of Gen Z changed medical education?

5. What do doctors and patients need to know to win the 4th industrial revolution? Organic chemistry?

6. How does the present system and its reliance on undergraduate STEM academic performance impact inequitable socioeconomic and demographic acceptance rates?

7. How should we transform premedical, medical, and post-graduate pedagogy? Examples are project-based learning and peer reviewed feedback.

8. Why do we insist that undergraduates declare a major?

9. Is the purpose of a medical school education solely to graduate students who have the knowledge, skills, abilities, and competencies to take care of patients, or should we provide them with exit ramps too?

10. How do we balance a medical culture of conformity with a culture of creativity?

11. What will be the future of medical work?

I’m lucky that I dodged the bullet. But I still have Plan B.

Image Credits: Adioma (Mark Vital), Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.
The Problems with ‘I’ll eat what you kill’ Arrangements​

The Problems with 'I'll eat what you kill' Arrangements​

GUEST POST from Arlen Meyers, M.D.

As more health professionals get involved with biomedical and clinical innovation and entrepreneurship, some are becoming advisors, mavens, salespeople, consultants and connectors. As such they are hired to help potential clients or employers meet benchmarks or the next critical success factor. In many instances, that means finding investors or helping to raise money for their early-stage company, newco or startup.

The success fee model also applies to sales and marketing, where the advisor is hired to source leads, leverage their relationships and networks and work around the gatekeepers of decision makers. They only get paid if contacts eventually buy the product.

Most say they do not have money to pay a retainer or recurrent cash payment so, instead they offer equity or some form of incentive or success fee model. Unfortunately, if you are considering such an “I eat what you kill” model, it comes with some problems:

  1. You might be running afoul of SEC regulations concerning raising private money if you are not a registered broker dealer
  2. If you are compensated with equity, the vesting schedule and amounts may not be mutually agreeable
  3. The company might not have the business development, sales operations, CRM or customer success infrastructure or people to follow up on leads and convert them to investors and track them back to you
  4. The client does not give you regularly scheduled updates on performance
  5. The client has unrealistic expectations about your ability to raise money from members of your network
  6. The client does not have a valid fundraising plan with the appropriate target investors
  7. After making an introduction or handoff, the result is no longer related to your efforts, much like a dating service
  8. There may be conflicts of interest for the advisor
  9. You may damage your reputation or personal brand if you are not transparent about your role
  10. You may not have the necessary education, skills, attitudes and competencies to raise money

11. The company or CEO you work for does not have the infrastructure, people or knowledge to close deals that you have sourced or people you have referred. Here are some reasons why and what they can do about getting a bigger ROI on their digital marketing tactics.

If you are asked to help a startup raise money, keep these issues in mind before agreeing to negotiated terms and conditions. Better to find your own meals than relying on eating what someone else kills.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

The Reasons Physicians are Losing the Branding Wars

The Reasons Physicians are Losing the Branding Wars

GUEST POST from Arlen Meyers, M.D.

Maybe the last time you walked into a retail-based clinic, you did not see an MD. Maybe the same thing happened at your hospital outpatient clinic or an urgent care center. Physician “extenders” and advanced practice professionals, like primary care pharmacists, nurse practitioners and physician assistants are winning the war on branding. They and their professional associations have done a good job branding their services while complacent doctors have not. What happened? Doctors are now “providers”. The latest spin is to call yourself a surgicalist. A surgicalist is a highly trained, board-certified surgeon who provides emergency surgical care within a dedicated hospital setting – the foundation of a surgical hospitalist program. A surgicalist career path affords talented surgeons the chance to design the life they want.

Staffing shortages among healthcare providers are having numerous downstream effects on everything from patient care to reimbursement and thinning margins. But they’re also causing a shift in public perception: More people now trust pharmacists to play a larger role in their care management, according to new research from Columbia University Mailman School of Public Health in New York City and Express Scripts Pharmacy.

With more than half (51.8%) of the U.S. population experiencing at least one chronic condition, and one-quarter suffering from multiple chronic conditions, prescription medications are often the first line of defense to help patients manage these conditions, the report found.

In the period from 2015–2018, nearly one-half of the U.S. population was using at least one prescription drug, nearly one-quarter (21.4%) were using three or more, and over 10% were using five or more prescription drugs.

All of that is putting pharmacists in the spotlight – along with the rise of chronic disease, increased medication use and shifts to value-based payment models.

Doctors don’t understand that branding a service, particularly one that is becoming more and more commoditized, is not like branding a product, like toothpaste. There are four keys to branding a service:

1. Don’t Mass Market To Your Target Market Take a look at the doctor ads. They are filled with platitudes like “quality care”, “personalized service” and “caring staff”. I would sure hope so. But, marketing to the masses with platitudes is like a CPA saying “I can do your taxes”. Instead, you need to “touch” your patients with highly targeted messages.

2. Focus On Relevance Over Differentiation Most product branding is about cheaper, smarter, faster, better compared to the competition. Service branding is about how I can solve your unique problem.

3. Worry About Growing Revenue, Not Market Share. Payer mix is an obvious difference when it comes to sickcare branding compared to product branding. As we all know, doctors don’t make the same profit seeing all patients. Some, in fact, are loss leaders. Soon, all of sick care might be a loss leader.

4. Help Your People Be Your Brand. Particularly in sickcare, your people are your brand, including the doctors. You are the product, not the doctor.

When it comes to these four elements, non-physicians are doing a better job than physicians and they are building brand equity. Take a page out of the FedEx playbook, and expect to see

  • A genuine and defensible market position
  • Improved external awareness, perception, and desirability
  • The development of a collaborative internal culture
  • Alignment and integration of all messaging
  • Revenue growth

Here are 10 ways to beat Commodity Care. For doctors to brand their services and win as incumbents in the market, they need to practice Othercare .

In the face of competition, substitutes and turf wars, doctors need to do more about their sustainable competitive advantage, particularly when it comes to practicing at the top of their license, building brand equity and innovating, all things that, up to this time, they have not done because they didn’t have to.

Maybe then, they won’t call you a provider anymore, doctor.

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.
The Seven P’s of Raising Money from Investors

The Seven P's of Raising Money from Investors

GUEST POST from Arlen Meyers, M.D.

Budding sickcare entrepreneurs inevitably want to know, “How do I raise money for my idea?” Most of the time, they are not ready for fundraising prime time and they have not taken the necessary steps to begin to do so or understand when and if it is the prudent thing or right time to do.

Here are the 7 P’s of raising money from investors:

1. Preparation

You should prepare to raise money by 1) derisking your idea as much as possible and 2) understanding what it will take to raise money i.e. technical, clinical and commercial (traction) validation.

When you have an exciting new idea, it’s easy to focus on all its benefits and jump to action. But doing so can lead to failure. Your limited perspective may mean you’re not seeing potential hurdles — and you may be leaving other promising options unexplored.

If you want the best ideas to flourish, you need to open your mind to different people from people beyond your team, whom you don’t usually talk to — and ask open-ended questions. After presenting your idea, ask: What stands out to you, and what’s missing? What would our critics say? Consider the failure of your idea: What would your premortem reveal? Consider other people outside the room and ask: What would someone on the frontlines say? Finally, put yourself in your competitors’ shoes. What flaws or weaknesses in your idea would they celebrate if you were successful?

  1. Do you understand the regulatory requirements and rules for raising private money?
  2. Do you know how much money you should raise and in what form: debt, diluting funds or non-diluting funds, like grants, contracts or some proof of concept awards?
  3. Have you validated the underlying hypotheses of your business model and demonstrated product-market fit? Do you have traction? What is the evidence? But, is product-market fit really enough?
  4. Do you have a reimbursement or revenue plan?
  5. Do you have a plan to create and protect your intellectual property?
  6. Do you have a regulatory approval or compliance plan?
  7. Have you created the appropriate corporate entity and corporate governance documents?
  8. Are you prepared to bootstrap your startup and dedicate the time, effort and capital required to be successful?
  9. Have you created the necessary fundraising and marketing collateral like a website, executive summary, social media channels to create awareness, engagement and buzz about your company?
  10. Can you answer these three questions: Is the market for the problem you want to solve big enough to make your journey worth it? How many customers want it and are willing and able to pay for it or get someone else to pay for it? Can you win at it give market competitors?

2. Plan/Strategy

After answering these questions, assuming you decide to proceed, you will need a capital raising plan and strategy. A capital raising strategy is essentially a roadmap for how your organization will pursue and obtain the funds it needs to fuel its growth. The capital raising process can take a long time and it’s a serious undertaking. However, while you may stay up late at night searching for new investors, writing pitch decks, and pouring over financial spreadsheets, building your strategy is the simplest part of the entire process. Here are the parts to the plan.

3. Pitch deck

Your pitch deck should tell your story. Who are the villains? Who are the heros? How did they win? There are many resources available to help you craft and polish your short, medium and long pitches, depending on the circumstances and the audience. Here is something to start:

4. Platform

You will need a CRM or tracking platform to keep track of the people who have contacted and how you intend to convert them as leads to investors. Crowdfunding platforms are another resource.

5. People

Do you have the right people on your startup team who can raise money? Are the founders the right people to do it? Do you have robust enough networks and contacts? Do you need a fractional of full-time accountant, controller or chief financial officer?

6. Process

The process should describe how and who will execute your fundraising plan, whether you are starting a company or scaling one. Since what you are doing is selling and marketing your idea and your team, what is your marketing, sales operations and sales enablement process?

7. Performance indicators

Performance indicators help you measure your progress and inform your strategy and execution adjustments moving forward. Here are some fundraising metrics for non-profits.

Raising money from investors is a lot like renovating your kitchen. It will take much longer than you thought it would, the costs in time, money and effort will be much bigger than you assumed and, when you see the final results, you will wish you had done some things differently.

Good luck and be sure to follow the right rainbow.

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Why Diversity and Inclusion Are Entrepreneurial Competencies

Why Diversity and Inclusion Are Entrepreneurial Competencies

GUEST POST from Arlen Meyers, M.D.

A competency is the ability to do something successfully. There are many entrepreneurial competencies. One of them is interdisciplinary teamwork and collaboration i.e. the ability of individuals to form partnerships with a team of professionally diverse individuals in a participatory, collaborative, and coordinated approach to share decision making around issues as the means to achieving improved health outcomes .

In the public health world, D & I means dissemination and implementation i.e. how does a intervention come into common use or become the standard of care. Here is what you need to know about it.

In the education and student success world, D, E & I means diversity, equity and inclusion. Here is the case for it.

In the entrepreneurial world, D, E & I is even more expansive and is measured by:

  1. Your ability to lead high performance teams both face to face and virtually
  2. How you create psychological safety – Here are four ways to boost psychological safety.
  3. The composition of your teams
  4. International representation
  5. Demographic representation
  6. Functional representation (marketing, engineering, finance, etc)
  7. Results
  8. Persona representation: coaches, teachers, cynics, mentors, etc
  9. Listening to both good rebels and bad rebels
  10. The people on your leadership team, advisory board and board of directors
  11. How you incorporate ideas from industries outside of your own. Sickcare cannot be fixed from inside.
  12. How you avoid bias and noise to influence outcomes and variability in decision making.
  13. How you avoid colorism in your sales and marketing approach.
  14. Ownership, not just fairness
  15. Improving your emotional intelligence along the narcissistic-empathy spectrum

Measuring the results or your efforts requires people analytics.

Are you ready to innovate?

I’m a privileged, old white guy who won the ovary lottery. My child of immigrant, first generation to college father got an advanced degrees. Consequently, I was able to grow up in the right ZIP code and take advantage of the opportunities afforded to me by sheer dumb luck. As a result, I wound up being an academic surgeon and worked at the same place for 40 years until I retired as an emeritus professor to pursue my next encore side gig, including working with several non-profits that sit at the intersection of sick care, higher education, biomedical and clinical entrepreneurship and diversity, equity and inclusion.

Four key arguments make the case for diversity, equity, and inclusion.

What are the barriers to leading DEI?

Rather than making leaders solely responsible for their own effectiveness, these researchers allow a balance between managerial competences and the many constraints that limit leaders. With bounded leadership, they look past the leader’s characteristics and consider the many constraints they encounter at the individual, team, organizational and stakeholder levels.

In bounded leadership, there are five distinct abilities leaders require to be effective:

  • Anticipation competence: The ability to predict market patterns and conditions, which are essential to the organization, such as future trends or customer needs
  • Mobilization competence: The ability to inspire employees to put an extraordinary effort into their work
  • Self-reflection competence: The ability to analyze past experiences and draw useful conclusions
  • Values-creation competence: The ability to promote a leader’s values in the organization
  • Visionary competence: The ability to create an attractive vision of the organization, communicate this vision to followers and empower them to implement it

Each of these competencies presents several hurdles: cultural (difficulties in changing values and norms), emotional (strong negative emotions that prevent rational behavior), entitlement (formalized organizational responsibilities and hierarchy), ethical (leaders’ dilemmas), informational (difficulties in processing or collecting data), motivational (problems with inspiring others) and political (office politics and power plays).

Competencies are measured by entrustable professional activities defined by a performance rubric. Creating diverse, equitable, inclusive teams that deliver expected results is one of them. But, getting from said to done takes more than education, training and policy changes.

Being DEI competent is not about changing your mind. It requires changing your mindset.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.
