Author Archives: Arlen Meyers

About Arlen Meyers

Arlen Meyers, MD, MBA is an emeritus professor at the University of Colorado School of Medicine, an instructor at the University of Colorado-Denver Business School and cofounding President and CEO of the Society of Physician Entrepreneurs at www.sopenet.org. Follow along onSubstack.

The 3 Student Entrepreneur Personas

The 3 Student Entrepreneur Personas

GUEST POST from Arlen Meyers, M.D.

Healthcare professional schools, healthcare innovation and entrepreneurship education, and training programs are growing. However, one question is should they be required or elective?

The medical student persona has changed in the past several years. Seeing around corners is always hard. However, to go to where the puck will be is a useful step when planning strategy and tactics to meet the needs of customers segments. Here are some ways to help build your parabolic mirror view of what’s next.

If you have a product or service and are planning not just for the now, but the next and new, then painting a picture of your customer archetype or persona is a key tool.

Do you know who your dream customer is?

There are three steps for understanding your dream customer:

  1. Consider the big issues they are facing – look wider and investigate global issues, such as hunger, environmental sustainability or education.
  2. Identify the industry trends that are affecting them – technology, big data, cyber security, etc.
  3. Describe your customer avatar/archetype/persona now – make a collage including their goals and values, demographics, their pain points and challenges.

Here are the various sickcare innovation and entrepreneurship student segments.

That said, the argument for mandatory is that all students should be exposed to core concepts, like design thinking, much like rotating through core clinical rotations, if nothing else, to get exposure to potential career choices. It might even make them better doctors and possibly help with burnout.

The argument for elective is that all students won’t have the same interests and it would be a waste of time and resources leading the laggards to water knowing you can’t make them drink.

One way to sort potential students is to understand the entrepreneurship education customer segments and their 3 core personas.

The Convinced and Confident know entrepreneurship should be part of their career pathway. In fact, many of them have had entrepreneurial life experiences prior to medical school.

The Curious but Clueless don’t know what they don’t know but are willing to learn more. Many have never held a job in their life. Some might be willing, but unable to develop an entrepreneurial mindset. Others discover their innerpreneur, and move on.

The Could Care Less are unwilling and unable to give it a try. Their attitude is , “I went to medical school to take care of patients, not take care of business”. What they don’t realize is that if you don’t take care of business, you have no business taking care of patients.

Here is what I learned teaching sickcare innovation and entrepreneurship to 1st year medical students.

Here is what I learned teaching sickcare innovation and entrepreneurship to a cohort of xMBA/HA students.

If you are part of creating or teaching these programs, you will eventually have to sort the wheat from the chaff. If you are a leaderpreneur, your job will depend on doing so.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

17 Reasons Not to Be a Physician Entrepreneur

17 Reasons Not to Be a Physician Entrepreneur

GUEST POST from Arlen Meyers, M.D.

Judging by the headlines on their LinkedIn profile and their presence on social media, more and more MD/DOs are innovators, coaches, entrepreneurs and non-clinical consultants. Many are starting or working with biomedical and clinical startups, including a group of medical school graduates, who don’t do a residency or starting their own company.. But:

  • They are not trained to do so
  • Entrepreneurship in the US has been in a downward spiral in the US for the past 40 years.
  • Most startups will fail
  • Most startups don’t have money to pay people
  • There is an innovation bubble.
  • Job security is low
  • You have to deal with people who have entrepreneurial psychopathologies are simply untrustworthy.
  • Students loan burdens are rising
  • Many are not in it for the long run
  • There are unrealistic expectations on both the consultant/employee and employer side.
  • Most MD/MBA programs should be terminated
  • Innovation theater is pervasive.

What is physician entrepreneurship? Entrepreneurship is the pursuit of opportunity under volatile, uncertain, complex and ambibuous conditions (VUCA).. The goal of physician entrepreneurs, is to create user defined value through the deployment of innovation using a VAST business model to accomplish the quintuple aim. There are many ways to do that other than creating a company.

Here are some reasons why you should think twice about being a physician entrepreneur:

  1. You are not ready to innovate
  2. You do not have the courage to innovate
  3. You do not have the mindset to innovate
  4. You think that your clinical mindset and your medical degree and training is enough to succeed
  5. You are not in a financial position to take the risk
  6. You are doing it to get away from someone of some job instead of towards something that is a better fit
  7. You do not have a career transition strategy
  8. You or your family are not willing to pay the price of successive failure
  9. You are unwilling to come down off the mountain
  10. It’s not personal
  11. You are not ready to quit your day job
  12. If you decide to create a company, or work for one, making money for the company is not that important to you.
  13. You don’t have the knowledge, skills, abilities and competencies to add value to a business
  14. You don’t have entrepreneurial DNA
  15. You don’t have a big enough network or know how to manage it as part of building your personal brand
  16. You don’t know how to sell things
  17. You are a problem solver, not a problem seeker.

Think twice about telling someone to take your white coat and shove it. You will save yourself and lots of other people heartburn and other people’s time, effort and money.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

The Lost Tribe of Medicine

The Lost Tribe of Medicine

GUEST POST from Arlen Meyers, M.D.

I can remember opening my medical school acceptance letter. I was, of course, excited to go down a lifelong career pathway, but also, felt joy at knowing that I was accepted into a tribe of international doctors that would welcome me anywhere in the world, who spoke a common language and had a common culture and ethos. A sense of community and belonging is important to mental health.

Research has shown that when employees feel that they belong to a team or organization, they will not only tend to perform better, but also experience higher levels of engagement and well-being. But our feeling of belonging at work has become challenged over the past year as we’ve shifted away from in-person interactions and found ourselves relying on video calls and screen activities to stay connected.

Here is the painting I passed under on my way to class for the first two years at Jefferson Medical College (The Surgical Clinic of Professor Gross/ Thomas Eakins):

Jefferson Medical College

Here is a painting I passed in the halls at the University of Pennsylvania (The Agnew Clinic/ Thomas Eakins):

University of Pennsylvania

Here is the painting of William Osler I passed in the halls of Philadelphia General Hospital:

Philadelphia General Hospital

Here is portrait of Florence Sabin where I work now.

Florence Sabin

One of the preeminent medical and scientific minds of the early twentieth century, Dr. Florence Rena Sabin (1871–1953) was a public servant devoted to improving public health. As the first woman to receive a full professorship at Johns Hopkins University, Sabin was also a successful woman in the medical field at a time when the profession was still dominated by men. In addition to helping Colorado’s fight against polio and tuberculosis, Sabin championed legislation that created the State Health Department in 1947 and successfully lobbied for a variety of other public health improvements. She is regarded as one of the best scientists Colorado has ever produced, and her legacy is honored with a statue in the nation’s capital.

Patrick Hanlon, is his book “Primal Branding”, defines a brand as something people feel something about. He goes on to state that believing is belonging. When you are able to create brands, like the medical profession, that people believe in , you also create groups of people who feel that they belong.

Primal branding is about delivering the primal code. Unlike the four elements of the code in DNA, though, there are seven: the creation story, the creed, the icons, the rituals, pagans, the sacred words and the leader.

Researchers have lumped tribes into 5 stages:

The reality is something else. Unfortunately, in many ways, the medical tribe has become fractious and unaccepting. The results are burnout, depression, suicide, disenchantment and fragmentation of power.

Examples include:

1. Medical education and training that some have described as abusive
2. Turf wars
3. Jealousy, greed and resentment for those who want to upset the apple cart, potentially threatening the cash cow and status quo
4. Marginalizing disruptive doctors
5. Subconscious or implicit bias against colleagues based on race, gender or other factors.
6. Hostility between MD and non-MD “providers”
7. Pushback against scope of practice creep
8. Specialists v generalists
9. Grunts v physician executives and administrators
10. Conflicts in interprofessional relations and care teams.
11. Racism. Is your doctor a racist?
12. Gender pay gaps

Here are 10 reasons why doctors don’t play nice with others.

Plus, all doctors have multiple affiliations and are more engaged with some than others. For example, they have varying levels of engagement with their employer, their specialty association or their local, regional or national medical association. Most tend to go where they are treated best and drop or ignore the others. Mentors,sponsors,coaches and colleagues help with burnout.

Many of us recall with fondness, particularly those who have served in the military, those times we shared with “foxhole buddies” e.g residency training, project teams, shock and trauma units and circumstances, like following mass killings or natural disasters, when the community comes to together. Even the doctor’s lounge is a thing of the past because the real estate is “too valuable” and doughnuts and coffee costs too much.

In many places, doctors have lost their sense of community and attachment to the tribe. The dark underbelly of medicine has damaged the brand.

When was the last time you visited the Museum of Physician Happiness?

Some solutions are:

1. Physician leadership academies that emphasize monitored experiential learning throughout medical school and residency
2. Reform the toxic culture of medical education and residency
3. Hold department chairs and deans accountable
4. Empower physicians to regain control of their destiny
5. Save private practice
6. Regulate overreach of private equity and corporate consolidation
7. Physician innovation and entrepreneurship fellowships
8. Kill most MD/MBA programs
9. Demand interprofessional cooperation or coopetition
10. Teach doctors how to rebuild the medical brand

We should also show more appreciation for each other.

Doctors have lost their sense of belonging. They don’t need a therapist. They need an anthropologist.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

Future of Global Physician Entrepreneurship

Future of Global Physician Entrepreneurship

GUEST POST from Arlen Meyers, M.D.

What’s your definition of entrepreneurship? Here’s the conventional one.

Mine is that physician entrepreneurship is the physician pursuit of opportunity under volatile, uncertain ,complex and ambiguous (VUCA) conditions with the goal of creating user defined value through the deployment of innovation using a VAST business model.

There are many myths about entrepreneurs. Here are some about physician entrepreneurs.

The life science innovation roadmap is risky, expensive and time consuming. To be successful, bioentrepreneurs whether healthcare professionals, scientists, engineers, investors or service providers, need to work as a team with their organizations to overcome the multiple hurdles taking their ideas to the market and patients. The process is neither linear nor predictable and outcomes are never guaranteed. In addition, because of global macroeconomic conditions, investors are unwilling to gamble on unproven technologies in a more hostile regulatory and legal environment. Consequently, commercializing bioscience discoveries is becoming more and more difficult. However, innovators still thrive. Where are some of these exciting business opportunities for bioentrepreneurs?

An initial understanding of the changes happening in international systems is the first step in identifying potential market opportunities. Here are but a few:

  1. Major and continual healthcare policy reforms
  2. Migration away from fee for service payment
  3. Consumerization, commoditization, internationalization, customization and digitization of care.
  4. Changing from a sick care system to a preventive and wellness system
  5. Defined benefit to defined contribution health insurance coverage
  6. Rightsizing the healthcare workforce
  7. Do it yourself medicine (DIY)
  8. Mobile and digical (physical and digital) care delivery models
  9. The growth of employed physicians
  10. Innovation management systems and increasing attention to health entrepreneurship.
  11. Increasing demand for high touch care
  12. Increasing discontinuity of cares changing quickly. All of these changes present biomedical and healthcare entrepreneurs opportunities to create new products, services, models and platforms. Patients are taking more control of funding and contributing to basic and clinical research using the internet and social media continues to play a bigger and bigger role in healthcare marketing and delivery.
  13. Demographic and economic changes and social mobility
  14. Closing the digital divide
  15. The impact of the 4th industrial revolution

Take opportunities in AIntrepreneurship, for example, in India, China, MENA and Africa

The drivers of physician international entrepreneurship include:

  1. Fear: Doctors are afraid they will suffer the professional, personal and economic consequences if they don’t adapt to change
  2. Greed: Physician incomes are threatened by innovation and new business models
  3. Necessity: Most doctors in industrialized countries have a relatively high standard of living. They did not bother themselves with innovation or entrepreneurship because they didn’t have to.
  4. The innovation imperative: The pace of change has accelerated and markets and employers are demanding more with less
  5. Generational demands: Medical students and residents are questioning their career decisions and demanding that schools provide them with the innovation and entrepreneurship education and training knowledge, skills and attitudes they need to thrive after graduation and throughout their careers
  6. The shifting doctor-patient relationship: Technology and DIY medicine is disintermediating doctors and fundamentally altering the doctor-patient relationship
  7. Resources: The internet, local ecosystems, acclerators and access to early stage capital has made it easier to start a business or develop an idea. People are connecting to the global economy.
  8. Portfolio careers: The sick care gig economy is growing and the future of work is changing. Fewer are committing to one lifetime career or job, including clinical medicine
  9. Opportunities: With change, comes opportunities and those few doctors with an entrepreneurial mindset are actively pursuing them. The opportunities in health entrepreneurship are sizable and physician entrepreneurs are increasing well positioned to capitalize on them.
  10. Culture: The culture of medicine is changing and encouraging creativity and innovation
  11. Politics: Access to quality care at an affordable price is in high demand as middle classes grow in developing countries. Not providing it leads to social upheaval and political instability.
  12. Budget deficits: The demand for care is almost infinite. However, the supply is limited. Consequently, policy makers and markets are looking for ways to improve outcomes at a lower cost through the deployment of innovation.
  13. Youth unemployment: Restless unemployed, educated citizens are demanding jobs and ways to use their talents.
  14. Economic development: Innovation and entrepreneurship is fuel that that feeds the engines of economic development in emerging economies. like Africa.
  15. Globalization: People, money and technology go where they are treated best, regardless of location.

The future of physician entrepreneurship is measured by progress in four domains: education, practice, research and impact. Unfortunately, each part of the physician innovation value chain is highly resistant to change and subject to multiple barriers to dissemination and implementation. We have made progress in all, but, the results are unevenly distributed.

The future of international physician entrepreneurship will be punctuated by:

  • The coherence of disparate technologies from diverse industries other than sickcare
  • Increasing transdisciplinary and international dependencies and collaboration
  • Educational reform in health professional, public health, bioengineering and computer science programs
  • Significant regulatory, legal, economic, ethical and societal issues
  • Generational, social and demographic variations in dissemination and implementation
  • An evolving global IT cybernervous system and interoperability
  • More difficult trust, privacy and security barriers
  • A high touch backlash against high tech
  • The rise of patient sickcare entrepreneurship
  • A slow migration to healthcare from sickcare

That said, this is the golden age of physician entrepreneurship, as reflected by the record number of applicants to US medical schools, the number of doctors pursuing non-clinical careers or side gigs, the ever increasing number of biomedical and clinical ecosystems, inclusion of digital health, business of medicine and entrepreneurship education and training in medical and graduate schools and the results and impact of entrepreneurs during the COVID pandemic.

Physician medical practice entrepreneurs, technopreneurs, intrapreneurs, social entrepreneurs, philanthropreneurs, edupreneurs and others are changing the world and the movement is spreading rapidly. Fortunately, despite efforts to the contrary, there is no vaccine to stop it.

Image credit: Unsplash

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

We need MD/MBEs not MD/MBAs

We need MD/MBEs not MD/MBAs

GUEST POST from Arlen Meyers, M.D.

The number of MD/MBAs graduating from medical schools continues to expand with about 5% of the roughly 20,000 US medical student graduates having dual degrees. While in past times the idea was to get the knowledge, skills, abilities and competencies to manage health services organizations, many are now doing it on the way to digital health startup land.

Most all of the 38 osteopathic schools offer dual degree programs as well.

However, MBA programs are dwindling and the ones that are still around are rethinking their value proposition and restructuring their curriculum.

For example, business schools are racing to add concentrations in science, technology, engineering and math to their M.B.A. programs as they try to broaden their appeal to prospective students overseas who want to work in the U.S.

Several schools, including Northwestern’s Kellogg School of Management and North Carolina’s Kenan-Flagler Business School, have unveiled STEM-designated master’s in business degrees in recent months. The University of California Berkeley’s Haas School of Business recently reclassified its entire M.B.A. program as STEM.

But, BMETALS is the new STEM.

In my view, we are training too many MD/MBAs that don’t add value to the system and that many programs should be terminated or restructured.

  1. We don’t know how much value the graduates contribute to the sick care system.
  2. The programs are usually not domain specific. Some think that’s a good thing, encouraging exposure to how other industries have solved generic problems. Others feel sick-care is so unique that the lessons are not applicable.
  3. Medical students are already up their waists in debt, most of which is taxpayer subsidized. Should additional debt be added to their student loans?
  4. Few of the programs address the needs of physician entrepreneurs.
  5. There are many substitutes for physician entrepreneurs around the world and US schools are no longer the mecca.
  6. Content has become generic and offered for free on the Internet.
  7. Connections are easy to make using social media.
  8. The MBA is losing credibility, given the large number of places that offer them, particularly those below the first-tier schools.
  9. Employers can see through the credentials.
  10. Costs continue to escalate and the programs do not accommodate the specific needs of busy clinician students.
  11. We need a thorough conversation about the policy wisdom of encouraging dual degrees, potentially side tracking graduates into non clinical roles when there is a global demand for clinicians.
  12. We need to track outcomes and roles of graduates to determine whether the dual degree adds value to the communities they are designed to serve and whether they are cost-effective in an era of skyrocketing student debt.

In addition, there is a difference between having knowledge, skills, abilities and competencies in the business of medicine, health systems science, health service organization management, leadership and leaderpreneurship and entrepreneurship/intrapreneurship. There is a confusing array of dual degree programs leaving students scratching their heads and, in many instances, wasting their time and money.

Also, more medical students are jumping ship to pursue non-clinical careers. While the numbers may a small portion of the roughly 20,000 first year US medical students, the trend is evident.

Instead, we should consider re-shuffling the deck and offer a new combined MBE (Masters in Bioinnovation and Entrepreneurship) degree or dual MD/MBE or PhD/MBE program.

According to Prof. Varda Liberman, the new Provost of Reichman University and Head of the MBA in Healthcare Innovation, “Healthcare systems are going through enormous changes worldwide and with the COVID-19, these changes were accelerated. There is an immediate need for a complete redesign that will necessitate innovative multidisciplinary solutions, leveraging technology, science, information systems, and national policy. Our MBA program in Healthcare Innovation, offered by Reichman University, in collaboration with Israel’s largest hospital, the Sheba Medical Center, Tel Hashomer, is designed to prepare the future leaders of the healthcare industry to develop solutions that will enable the needed redesign. The program brings together all the unique advantages of Israeli innovation, to provide our students with the tools and skills necessary to understand the complexity of the healthcare industry today. The program brings together all the key players of the ecosystem – those coming from the healthcare system, engineering, entrepreneurship, AI, law, biomedicine, pharmacology, high tech, investment, management, and public policy”.

Here’s how it would work:

  1. A four-year program combining two years in medical school and two years in an MBE program, patterned similar to Professional Science Masters Programs.
  2. The medical school curriculum would be separate and distinct from that offered to medical students interested in practicing medicine. Among other topics, we would teach sales.
  3. Clinical rotations should start on day one, intended to instill an entrepreneurial mindset and emphasize being a problem seeker, not a problem solver at this stage
  4. Interdisciplinary education with experiential learning in project teams that includes business, science, engineering, law and other health professionals.
  5. Experiential learning and a mandatory internship with local, national or international company in biopharma, medtech or digital health.
  6. A new tuition and funding structure, possibly run by private equity or medical technology companies who sponsor applicants. The present medical education business model won’t work if it depends on short term revenue by putting butts in the seats.
  7. Project teams would be offered proof of concept funding and iCorps team support
  8. Domain experts would work with project teams
  9. Each student would be assigned an entrepreneur mentor throughout the program
  10. Social biomedical entrepreneurship and ethics would be core streams throughout training. Those interested in creating non-profits or going into public service might be candidates for tuition deferral or waiver.

Another alternative is to make medical school 3 years instead of 4 and offer a one year track in biomedical and clinical entrepreneurship.

The good news for educators is that you don’t need to start from scratch. Karolinska beat you to the punch.

The purpose of the degree program is to provide students with the knowledge, skills and abilities they need to lead global biomedical innovation. Here’s what the curriculum would include:

  1. Building Biotechnology: Introduction to biomedical entrepreneurship
  2. Regulatory Affairs and Reimbursement
  3. Life Science Intellectual Property
  4. International (Bio) Business
  5. Biotech law and ethics
  6. Internship
  7. International trip
  8. Device and digital health entrepreneurship
  9. Leading high performance teams
  10. Bioentrepreneurial finance
  11. Drug discovery and development
  12. Care delivery entrepreneurship
  13. Social entrepreneurship
  14. Electives in other aspects of entrepreneurship

The David Eccles School of Business at the University of Utah is taking its top 10 ranked program for entrepreneurship to new heights with a master’s degree designed for serious entrepreneurs.

The degree is called the Master of Business Creation (MBC), and it’s the first of its kind.

Applicants must be full-time entrepreneurs who want to create, launch and scale a new business, who want more than the 9-to-5 job, who have the drive to overcome the impossible, who want to build their knowledge while doing, and who are willing to put in the hours to make it happen.

We don’t need more physician administrators. We need more physician innovators and entrepreneurs who can lead us out of our sick care mess and close global health outcome disparities. While I believe the optimal career track involves a reasonable time practicing clinical medicine, students are thinking otherwise. For those that do, they need a new path to creating the future and medical and business educators need to create educational products that meet their needs.

Image credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

What Makes Digital Health Clinical Trials Different?

What Makes Digital Health Clinical Trials Different?

GUEST POST from Arlen Meyers, M.D.

For digital health entrepreneurs, unless your intended use puts you in the FDA category of a medical device, you don’t need to show that your product is safe and effective, let alone cost-effective. In most cases, rather, you need to demonstrate to investors that it can quickly scale and make money and the sooner the better. Too bad. You would think that whether you have to or not that prudent sick care business practices would mean creating a product that does what you say it will do. That’s why only a handful of the hundreds of thousands of digital health apps are clinically valid.

However, most sick care digipreneurs avoid costly, risky trials because they are afraid of possible negative results that could be the death blow of their company, like many early stage biotech or device companies that wake up to see their valuations plummet due to a failed trial.

Digital health regulation is changing rapidly as the FDA tries to keep up with the pace of change and new products and services. On FDA regulation, the rule—for now, at least—is clear: Any device that is “intended for use in the diagnosis of disease of other conditions, or in the cure, mitigation, treatment, or prevention of disease” requires FDA approval, Curtis said. This goes for devices meant for humans and animals, as the FDA regulates both.

The emergence of digital therapeutics, the incorporation of AI and the adoption of remote sensing is challenging us how to demonstrate safety and efficacy, if not cost-efffectiveness.

For example, there’s been an explosion in the number and variety of digital apps purporting to address behavioral health issues, but a recent study published in Nature Digital Medicine casts doubts on their backing by legitimate scientific research. Based on the literature review conducted by the researchers, only 14 percent of apps described design or development that was based on real-world evidence.

One commentary to a recently published article on digital health trials noted that “The pipeline of digital health studies appears to be promising,” noted the researchers, but they also underscored that the small sample sizes in many studies “could limit their ability to yield a high level of evidence, demonstrate value, or motivate stakeholder adoption.”

Digital health technologies hold great promise to solve some of the biggest problems in our healthcare system, including achieving higher quality, lower cost, and greater access to care. a better doctor and patient experience and efficiencies in business processes. In the January 2019 issue of Health Affairs, reported that scant evidence exists demonstrating the clinical impact of twenty top-funded digital health companies. These companies tended not to study the clinical effectiveness of their products in terms of key healthcare metrics like patient outcomes, cost, and access to care.

They found 104 peer-reviewed published studies on the products or services of these companies. The majority of the studies were from three companies. Nine companies had no peer-reviewed publications. Only 28% of the studies targeted patients with high-burden, high-cost conditions or risk factors. Healthy volunteers were the most commonly studied population. Further, 15% of all studies assessed the product’s “clinical effectiveness” and only eight studies assessed clinical effectiveness in a high-cost, high-burden population. The eight clinical effectiveness studies measured impact in terms of patient outcomes, while no studies measured impact in terms of cost or access to care. There were no clinical effectiveness studies in heart disease, COPD, mental health conditions, hyperglycemia, or low back pain. Studies that did not assess clinical effectiveness may have intended to validate the product against a gold standard measurement or report feasibility of use.

This is of particular interest given the incredible amount of funding, interest, and hype in digital health. Although these companies were only a small portion of total digital health companies, they were a large portion of total private funding and had the most resources to demonstrate impact. Further, since “digital health” currently encompasses myriad technology types and approaches, these findings have broad implications.

From text messages to mobile apps, digital health devices are becoming increasingly important in clinical trials for their ability to streamline trials, lower site burden, and improve the patient experience. However, manufacturers must consider the safety, reliability, and convenience of these devices in order to effectively implement them into medical device trials. The digital components of these medical device trials must adhere to the same rigorous regulatory standards as the device itself, which can pose significant hurdles for some sponsors. Those hurdles include:

  • Usability and Accuracy. Sponsors must be able to determine that a device is providing the desired endpoint values in a trial. The metric should be accurate and presented in a usable format.
  • Safety. The manufacturer should be able to provide highly secure methods for transmitting data between the digital health device and the analysis site.
  • Convenience. The manufacturer should be able to provide logistical support to decrease the site and subject burden. They should also be able to provide full documentation of engineering verification for the devices.
  • Ease of Use. It is important to consider how the patient will interact with the device. It needs to be an appropriate size and weight, and it should allow the patient to move and behave in the same way he or she normally would.
  • Reliability. To maintain data continuity, the device should have a battery life sufficient to allow it to collect data for long periods of time with minimal glitches.

In another study of digital health apps for COVID 19, apps were evaluated using the Systems Wide Analysis of mobile health-related technologies (SWAT) tool in line with the NHS Digital Assessment Questionnaire and were given a score for each category (usability, functionality, ethical values, security and privacy, user-perceived value, design, and content) by two independent assessors.

A recent review concluded that “Safety of apps is an emerging public health issue. The available evidence shows that apps pose clinical risks to consumers. Involvement of consumers, regulators, and healthcare professionals in development and testing can improve quality. Additionally, mandatory reporting of safety concerns is needed to improve outcomes.”

The concept of a “digital clinical trial” involves leveraging digital technology to improve participant access, engagement, trial-related measurements, and/or interventions, enable concealed randomized intervention allocation, and has the potential to transform clinical trials and to lower their cost. In April 2019, the US National Institutes of Health (NIH) and the National Science Foundation (NSF) held a workshop bringing together experts in clinical trials, digital technology, and digital analytics to discuss strategies to implement the use of digital technologies in clinical trials while considering potential challenges. This position paper builds on this workshop to describe the current state of the art for digital clinical trials including (1) defining and outlining the composition and elements of digital trials; (2) describing recruitment and retention using digital technology; (3) outlining data collection elements including mobile health, wearable technologies, application programming interfaces (APIs), digital transmission of data, and consideration of regulatory oversight and guidance for data security, privacy, and remotely provided informed consent; (4) elucidating digital analytics and data science approaches leveraging artificial intelligence and machine learning algorithms; and (5) setting future priorities and strategies that should be addressed to successfully harness digital methods and the myriad benefits of such technologies for clinical research.

But, when it comes to human subject pilots and trials, there are several glaring differences of digital health trials compared to drug and device trials:

  1. Intellectual property concerns are usually lower in digital trials
  2. Digital trials need to be done faster because the markets change so quickly and the barriers to entry are lower
  3. IRBs set up to protect patients in drug and device trials are not comfortable with digital health trials
  4. We are still trying to define the ethics of data science
  5. Cybersafety is as important as patient safety
  6. Digital health clinical trial ecosystems are primitive compared to drug and device trial ecosystems although both have recruitment and completion challenges
  7. Data trials need mostly patient data, not the physical presence of patients
  8. HIPAA rules get in the way
  9. Lack of interoperability and getting data from non-traditional hospital based HIT systems skews the data and , consequently, the results
  10. Funding sources for conducting digital health trials are scarce. Investors don’t fund research projects. They fund product development and marketing. Here are some ideas on how to convince your CFO to pilot, test and integrate your IT solution.

The FDA has stated their position when it comes to the regulation of mobile medical apps.

Digital health has evolved because:

  1. Interoperability is improving
  2. Sick care is turning into health care
  3. The medical business model is changing
  4. Costs continue to spiral out of control
  5. The recognition by digipreneurs and investors that sick care is ripe for digitization
  6. Patient and provider frustration with a lousy experience
  7. Cheap mobile and internet technologies
  8. Regulatory, IP and reimbursement changes
  9. The breakdown of barriers to diffusion and implementation
  10. Digital heath ecosystems

An international consortium of medical experts has introduced the first official standards for clinical trials that involve artificial intelligence. The move comes at a time when hype around medical AI is at a peak, with inflated and unverified claims about the effectiveness of certain tools threatening to undermine people’s trust in AI overall. 

Collaboratively developed guidelines for the privacy, content, security, design and operability of mobile health (mHealth) apps have been released. Compliance with the guidelines can provide a level of assurance that an app delivers value to patients, physicians and other users.

The guidelines were developed by Xcertia, a nonprofit founded by the AMA and other major health and technology organizations. They address concerns that have hindered the use of mHealth apps. Fears that an app may expose personal health information, that its content is inaccurate or that its functionality is limited have slowed adoption of mHealth digital health tools.

These advances are permeating all aspects of clinical research but the recent acceleration of decentralised and hybrid clinical trials (DCTs) illustrates how far reaching digitalisation is becoming. Patient-centricity has been driving the decentralisation of clinical trials for some time but the rapid emergence of the COVID-19 pandemic required the pharmaceutical industry to pivot operations and accelerate its DCT programmes. This response required a corresponding ramp-up in mobile technology, data management and AI.

AI can provide insight into protocol complexity and contribute to protocol designs better adapted to DCTs, including the creation of virtual control arms. The intelligent use of data to include historical data as well as the data collected during a clinical trial can optimise the number and diversity of patients needed to reach the desired endpoints and give the patients who do participate a higher value experience.

Until and unless we address ongoing digital health clinical trial issues , sick care digipreneurs will have little or no incentive to conduct digital health clinical trials using precious startup funds. Instead, they will continue to sell snake oil and lots of folks will buy it. Maybe you should sleep on it.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

The Gilded Age of SickTech

The Sicktech Gilded Age

GUEST POST from Arlen Meyers, M.D.

The WSJ reported that Twitter Inc. TWTR 5.66% accepted Elon Musk’s bid to take over the company and go private, a deal that would give the world’s richest person control over the social-media network where he is also among its most influential users.

The $44 billion deal marks the close of a dramatic courtship and a change of heart at Twitter, where many executives and board members initially opposed Mr. Musk’s takeover approach. The deal has polarized Twitter employees, users and regulators over the power tech giants wield in determining the parameters of discourse on the internet and how those companies enforce their rules.

In response, the NYT reminded us that two years ago, the economists Emmanuel Saez and Gabriel Zucman published a statistic that you don’t normally see. It was the share of wealth owned by the richest 0.00001 percent of Americans.

That tiny slice represented only 18 households, Saez and Zucman estimated. Each one had an average net worth of about $66 billion in 2020. Together, the share of national wealth owned by the group had risen by a factor of nearly 10 since 1982.

Wealth inequality in the US is rising with fewer and fewer owning more and more. As digital health consolidates and unicorns become as common as dandelions on your lawn this time of year, should we fear the Sicktech Gilded Age? What are the concerns?

  1. Will these technologies cause more problems than they solve?
  2. With wealth comes power. What will that mean for equitable access?
  3. What will be the impact on the business of medicine?
  4. Will profits precede patient interests more than they are now?
  5. What will be the impact of private equity on medical practice?
  6. How should we educate and train health professionals to work in the Sickcare Gilded Age?
  7. How will sickcare entrepreneurs respond?
  8. What will be the backlash from the sickcare workforce? Labor actions and strikes?
  9. How much more will the prices of sickcare rise as inflation eats away at household spending?
  10. Will technobarons be able to transform sickcare into healthcare?
  11. Will there be a Luddite backlash? The past is prologue.
  12. What will be the impact of sickcare technologies on society?

Or, will there the bubble pop and we will start seeing more “cram downs”? Do you trust sickcare technobarons to do the right thing?

We will have to wait and see whether Mr. Musk can unleash the value of Twitter or whether sickcare barons can do the same. Many other billionaires have failed trying.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

The Entrepreneurial Mindset

Have you seen the entrepreneurial mindset framework for innovation leaders?

The Entrepreneurial Mindset

GUEST POST from Arlen Meyers, M.D.

Most doctors, scientists, engineers, business school grads and lawyers I’ve taught don’t have an entrepreneurial mindset. There are lots of reasons why, some of which have to do with how they are chosen by their respective educational establishments. After all, you don’t get accepted to medical school because of your intense creativity. You get accepted, primarily, because of your GPA ,your performance on a standardized test, the MCAT, and how you perform in your scripted interviews.

Here are some mindset maps from Kevin Johnson:

  1. All risk isn’t risky. Entrepreneurs surely understand the high probability of failure, but they don’t necessarily like to gamble. Instead, they take calculated risks, stacking the deck in their favor. They must have enough confidence in themselves, supplemented by expert knowledge, solid relationships, or personal wealth, to see the risk as near zero.
  2. Business comes first, family second. This view isn’t a selfish one, but a recognition by serious entrepreneurs that family well-being is dependent on the success of the business, not the other way around. This is why airlines ask you to put on your oxygen mask first. Should you forego closing a million dollar deal to attend a ball game with your son?
  3. Following your passion is bogus. Look for a good business model first. Your passion may be for a good cause, like curing world hunger, but it may not be a good business. In any young business, you inevitably find things that are not enjoyable, but need to be done, like cold calls or firing unproductive employees. Just doing fun things is a myth.
  4. It’s not about being your own boss. Great entrepreneurs aren’t interested in being bosses at all. People who crave the freedom to do what they want when they want generally make terrible entrepreneurs. In order to be a successful entrepreneur, discipline is a must, and accept your new bosses as investors, partners, and customers.
  5. Fire your worst customers. We have all had customers who take advantage of us, to the detriment of other good customers. The best entrepreneurs are quick to make the tough decisions to bypass bad customers, with proper respect, to minimize frustration, resource drain, and reputation loss. You can’t please everyone all the time.
  6. Ignorance can be bliss. It’s great to be highly familiar with the industry in which you plan to compete, but many times people see too many challenges, and never start. In other cases, entrepreneurs are opening up new business areas, so no one yet knows the challenges. Serious entrepreneurs trust their ability to beat a new path to the opportunity.
  7. You’re in no rush to get an MBA. If you are already an entrepreneur, more education, including an MBA, will only slow you down. Consider it a waste of time. If you plan to become an entrepreneur, and already have business experience or an undergraduate business degree, skip the two-year delay and cost of the MBA.
  8. You are odd, and it’s OK. Entrepreneurs, especially those in technology, usually don’t start out as well-rounded, well-adjusted leaders. In fact, being odd is quite the norm. According to other studies, attention-deficit disorder (ADD) is common, as well as host of other personality disorders. It’s actually cool to be a geek in this lifestyle.
  9. A check in hand means nothing. Every entrepreneur remembers their naïve days when that first customer check bounced. When you receive a new purchase order, a check, a verbal agreement, or even a written agreement, don’t get too happy and excited. Save the celebration until you have cold cash in hand, or the funds are verified.
  10. There’s no such thing as a cold call. If you are an elite entrepreneur, you don’t go into anything cold. With the Internet and a plethora of other resources, you can warm up any call quickly, and not waste your time or theirs. Doing your homework first is one of the best ways to get an advantage over your competition.

Instead, when it comes to innovation and entrepreneurship, they have this kind of frame of reference:

  • They don’t acknowledge they don’t know what they don’t know
  • They don’t understand the difference between a scientific or clinical mindset and an entrepreneurial one
  • They take no for an answer
  • They are insecure and lack self esteem when early in their careers and therefore feel obligated to compensate with dysfunctional behaviors, often encouraged by the culture of their training programs
  • They don’t take personal responsibility for their mistakes and , therefore, don’t learn from them
  • They think that what got them to where they are now will get them to where they want to go
  • They don’t think networking is important, so, they don’t do it
  • They are not politically savvy
  • They lack entrepreneurial courage
  • They lack access to mentors, knowledge, education, resources, peer to peer support and career development guidance.

The entrepreneurial mindset is a state of mind interested in the pursuit of opportunity with scarce, uncontrolled resources. The goal is to create user defined value at various multiples of the existing competitive offering through the deployment of innovation.

Some describe “character” as a combination of personality, which is mostly fixed at a certain early age, and mindset, which is malleable. Character is fate.

Attitudes and motivation are what separates someone with an entrepreneurial mindset from another. The field of postive psychology has shown with overwhelming evidence that happiness creates success, not vice versa. Shawn Achor, in his book The Happiness Advantage, gives us a guided tour of the postive psychology field. noting that happiness is a positive emotion in three measurable components: pleasure, engagement and meaning. He states that happiness is the joy we feel striving after our potential. More imporantly, mindsets can change in humans from negative to positive. Consequently, happy people are primed for creativity, imagination and innovation.

Innovation starts with the right mindset and happiness makes it easier to see things clearer as well as the possibilities.

Some have described the Innovator’s DNA. Here are the amino acids that make up the genetic code.

Others note characteristics of the entrepreneurial mindset:

  1. Personal growth relates to the size of the challenge, not the size of the kingdom. What motivates real innovators is the more exciting challenge, not the number of people reporting to them. The ‘size of the difference’ they will make is more inspiring than the ‘size of the business.’ They relish getting out of their comfort zone, and into the unknown.
  2. The new direction is the challenge, not the destination. The challenge is the transformation vehicle for true innovators, and not a performance goal. They focus on legacy creation, not legacy protection. They ignore failures and are constantly looking at the progress made. They treat innovations reviews like performance reviews.
  3. Be an attacker of forces holding people back, not a defender. Real innovators start by questioning the world order rather than conforming to it. They begin by confronting the forces holding everyone back, rather than living with it. The forces include mindset gravity, organization gravity, industry gravity, country gravity, and cultural gravity.
  4. New insights come from a quest for questions, not a quest for answers. This discovery mindset searching for new questions drives real innovators away from more of the same. They fundamentally become value seekers; they look for value in every experience, in every conversation. They don’t seek prescriptions, they seek possibilities.
  5. Stakeholders must be connected into the new reality, not convinced. True innovators tip stakeholders into adopting and even co-owning the orbit-shifting idea. They go about tipping the heart first, assuming the mind will follow. They seek smart people, who openly express their doubts, and then collaborate to overcome them.
  6. Work from the challenge backward, rather than capability forward. Overcoming execution obstacles is combating dilution, not compromising, for these innovators. Their mindset is not ‘if-then’ but ‘how and how else?’ They convert problems to opportunities, and often the original idea grows far bigger than the starting promise
  7. Getting rid of your victim mentality.
  8. Having the discipline to practice the discipline
  9. You relish the role of leading the charge. Being a visionary or an idea person is not enough; you have to be anxious to jump in and get your hands dirty. Most success stories in business are not about envisioning the next big thing, but about making that change happen. Investors and strategic partners look for entrepreneurs who can execute.
  10. Able to balance right-brain and left-brain activities. Most technical entrepreneurs are left-brain logical thinkers, even perfectionists. Yet every business today needs a focus on visualization, creativity, relationships, and collaboration, which are normally in the domain of right-brainers. Successful and happy entrepreneurs have that rare whole-brain focus.
  11. Enjoy being outside your comfort zone. New businesses are an adventure into the unknown. You need to be mentally prepared to enjoy the roller coaster ride, rather than face it holding your breath with your teeth gritted at every turn. Only then can you enjoy the thrill of victory when you survive a major turn, and be energized for the next one.
  12. Proactively seek input, but make your own decisions. Great entrepreneurs seek out critical customers and industry experts, and actively listen, but are not afraid to trust their own judgment as well. Ultimately they accept the responsibility of “the buck stops here,” meaning they live by their own decisions, and never make excuses.
  13. Willing and able to do a little bit of everything. Technology experts tend to have a very deep level of knowledge, but not very wide. If your real interests are not very broad, then building a business will likely be frustrating and expensive. Startups have limited resources, so the founders have to enjoy trying things, and learning from their mistakes.
  14. Viewed by others as a successful problem solver. The best ideas for a new business are solutions to a real customer problem, rather than great ideas looking for a market. Creating a new business means tackling one difficult problem after another, until success suddenly appears. Entrepreneurs see problems as milestones to success, not barriers.
  15. Don’t demand or expect immediate gratification. Seth Godin once said “The average overnight success in business takes six years,” and he is an optimist. For some entrepreneurs that success is financial, and for others it is a legacy of good deeds. Because it takes so long to get there, it is important to be happy with the journey.
  16. Having a growth mindset. That means experimenting and letting your passion find you instead of finding your passion. Here are some tips on how to develop your growth mindset-think like employee #3 at a startup.
  17. Optimism Research suggests that optimists earn more money, have better relationships and even live longer. And the thing is: Optimism can be learned.

Here are the 8P’s of the Entrepreneurial Mindset:
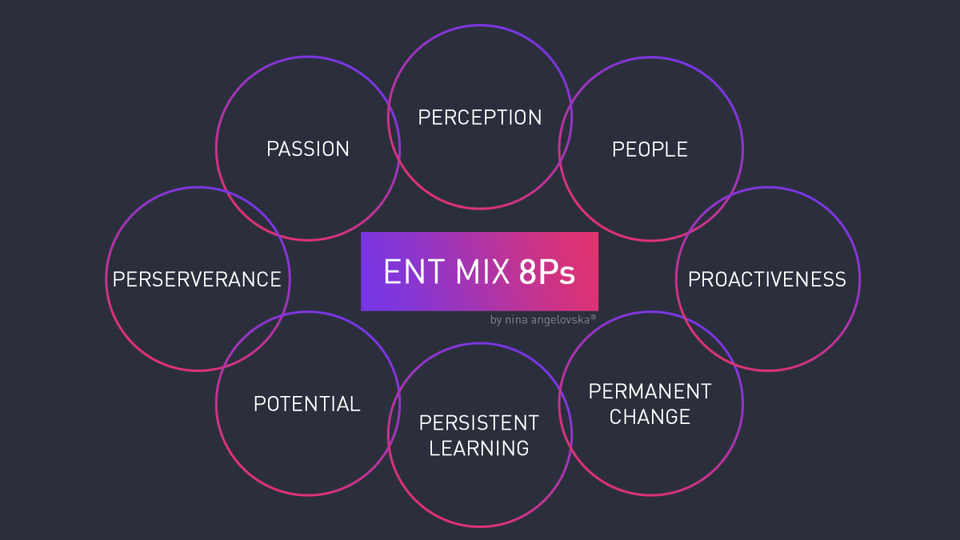
Eight P's of Entrepreneurial Mindset

Lately, the term “grit” is popular and describes the combination of passion and perseverance. The growth mindset is driven by curiosity and self-compassion.

Here’s how the entrepreneurial mindset differs from the clinical mindset. There are also age and generational variations, e.g. how to deal with ambiguity.

Entrepreneurial mindsets derive from entrepreneurial behaviors that are part of an entrepreneurial culture. Consequently, finding entrepreneurial champions to demonstrate the mindset to others is an important tactic in changing a culture.

True innovation in sick care is rare. Ideas and inventions rarely create substantial multiples of user defined value and can be counted on one hand. Antibiotics. Anesthesia. Clean water. Transplantation.

Here are some ways to look at the world through an innovative/entrepreneurial mindset:

Wonder about inconsistencies and anomalies instead of dismissing or explaining them away.

Wonder about coincidences that seem promising.

Give freer rein to curiosity, spending more time speculating about implications of events or ideas that aren’t on the main path we are pursuing.

Be alert to unexpected connections between ideas.

Notice leverage points that might help when we get stuck – alternative ways to move forward when our usual problem-solving methods aren’t working. Instead of simply making sure projects are progressing at a satisfactory pace, supervisors can ask employees more in-depth questions: How has your understanding of the project changed? What has surprised you? Are you tempted to change the project goals? If the employee responds that nothing has to be rethought, this may indicate that the person isn’t adopting the In/Stance. Confusions and conflicts may offer opportunities for gaining insights. Employees may have misconceptions of different ideas about how things work– Investigate these inconsistencies, as they may lead to insights.

Learning is about unlearning. Like every change, it requires unfreezing , changing and refreezing.

Of course determining how many of the roughly 900,000 active docs have an entrepreneurial mindset depends on how you define it and the instrument you use to measure it. Since few, if any, have done that, including search and placement firms, there is really no valid way to know.

Here’s an article that covers the landscape and attempts to measure the entrepreneurial mindset. Basically, personalities are fixed, but skills can be learned.

Personality Scales

Independence: The desire to work with a high degree of independence (e.g., I’m uncomfortable when expected to follow others’ rules.)

Preference for Limited Structure: A preference for tasks and situations with little formal structure (e.g., I find it boring to work on clearly structured tasks.)

Nonconformity: A preference for acting in unique ways; an interest in being perceived as unique (e.g., I like to stand out from the crowd.)

Risk Acceptance: A willingness to pursue an idea or a desired goal even when the probability of succeeding is low (e.g., I’m willing to take a certain amount of risk to achieve real success.)

Action Orientation: A tendency to show initiative, make decisions quickly, and feel impatient for results (e.g., I tend to make decisions quickly.)

Passion: A tendency to experience one’s work as exciting and enjoyable rather than tedious and draining (e.g., I’m passionate about the work that I do.)

Need to Achieve: The desire to achieve at a high level (e.g., I want to be the best at what I do.)

Skill Scales

Future Focus: The ability to think beyond the immediate situation and plan for the future (e.g., I’m focused on the long term.)

Idea Generation: The ability to generate multiple and novel ideas, and to find multiple approaches for achieving goals (e.g., Sometimes the ideas just bubble out of me.)

Execution: The ability to turn ideas into actionable plans; the ability to implement ideas well (e.g., I have a reputation for being able to take an idea and make it work.)

Self-Confidence: A general belief in one’s ability to leverage skills and talents to achieve important goals (e.g., I am a self-confident person.)

Optimism: The ability to maintain a generally positive attitude about various aspects of one’s life and the world (e.g., Even when things aren’t going well, I look on the bright side.)

Persistence: The ability to bounce back quickly from disappointment, and to remain persistent in the face of setbacks (e.g., I do not give up easily.)

Interpersonal Sensitivity: A high level of sensitivity to and concern for the well-being of those with whom one works (e.g., I’m sensitive to others’ feelings.)

It would be interesting to apply this to a physician population and compare to the general one.

Teaching and learning entrepreneurship is as much about nudging students to adopt an entrepreneurial mindset as it is teaching skills, particularly if they are narrowly focused on creating a business.

But, how do you reframe a mindset? Here are some tips on how to do it.

If we are to innovate our way out the the current “health” care system mess, we need to identify those with an entrepreneurial mindset and turn them loose on the most wicked problems that beset us. Marginalizing, stifling or channeling them into a limiting culture is a terrible waste of a mindset.

Image credits: Nina Angelovska, Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

19 Things Physician Entrepreneurs Don’t Get About Sales and Marketing

19 Things Physician Entrepreneurs Don't Get About Sales and Marketing

GUEST POST from Arlen Meyers, M.D.

Many biomedical and health marketing and sales people ask about tips and techniques on how to sell to doctors. But, very few doctors or physician entrepreneurs have much interest in how to market and sell to patients and other customers. The conventional wisdom goes that they are “too busy” or “don’t have the time” and that they are trained to take care of patients, not take care of business.

I disagree, as I’ve explained in many other posts. However, sales is not in the medical school course catalog.

During a pandemic, that is not an option. Here is what you need to know about digital marketing now.

Here are some social media strategies you should use in the post-pandemic world.

Do you know how to rank #1 on Google?

Ogilvy, one of the most respected marketing firms globally, has recognized this shift by stating that the traditional “4 Ps of Marketing” are out and the 4 Es are in.  

  • Experience is more important than Product
  • Everywhere (Omnichannel) is now Place
  • Exchanges outweigh Price
  • Evangelism is more valuable than Promotion

Here is the job description for a social media manager for Microsoft:

Responsibilities

  • Design and execute a slate of rich social media strategies that resonate with our diverse and global audience and drive its implementation across our key campaign moments.
  • Define social media priorities, set goals and targets, aligning with audience insights. Proactively identify areas of optimization, set best practices, and communicate these across teams.
  • Partner across MSR Labs, Campaign Marketing, Community Engagement, Comms, Editorial, and Web/Media Production to support opportunities for rich scientific storytelling.
  • Serves as a trusted advisor to senior leaders through strong communication and influencing skills.
  • Creates and presents business reports that outline impact driven and provides recommendations based on outcomes.
  • Ability to focus on business priorities and create boundaries to ensure successful project completion.
  • Work with the paid social media team to execute and deliver on overall campaign KPIs.
  • Continuously improve on results by capturing and analyzing the appropriate social data/metrics, insights, and best practices, and then work with marketing managers to execute on those KPIs and leading indicators.

Qualifications

Required Qualifications:

  • 5+ years of practical experience in a global enterprise social media environment or global agency in the field of social media.
  • Experience in the use of social media platforms (Facebook, Instagram, LinkedIn, Reddit, TikTok, Twitter, Twitch, YouTube, or Club House, etc.).

Preferred Qualifications:

  • Bachelor’s Degree
  • Exceptional formal and colloquial communications skills.
  • Ability to collaborate effectively within a team and across organizational and team boundaries.
  • Ability to manage complex projects in a fast-changing environment.
  • Proven track record for new, innovative approaches, and smart risk taking.
  • Understanding and natural curiosity of evolving social media trends.
  • Experience with tools like Sprinklr, Opal, Excel, and Power BI.
  • Positive attitude, detail and customer oriented along with strong multitasking and organizational acumen.

Here are 10 things docs don’t seem to understand about healthcare sales and marketing:

1. That they are different. Said another way, the marketing team figures out the strategy. The sales team executes the battle plan. Marketing serves the interests of the buyer. Sales serves the interests of the seller.

2. That they are complementary and have to be aligned

3. That the sales plan should not be an afterthought when building the business model canvas or business plan for a new venture.

4. That branding is not sales and marketing and that B2B marketing is different than B2C marketing.

5. That the Internet and social media have revolutionized how they both are done.

6. That service after the sale is just as important as selling the product and that they need to pay attention to the aftermarket.

7. That they don’t need to worry about any of this because they work for someone else who does it or they are busy enough.

8. That they should just outsource sales and marketing to someone else and just see patients.

9. That they can just depend on word or mouth referrals. It used to be docs played golf with their friends, but they now work on Wednesdays .

10. That all they need to do is hang a shingle to be successful because they have been reading about the shortage of doctors.

11. If you are a physician entrepreneur selling to doctors, you will relate to these tips on how to sell to doctors.

12. Every customer segment in sickcare requires a different value proposition, marketing and distribution/sales strategy. The 4Ps can rapidly become the 8, 16 or 24 Ps.

13. They actually believe they are the best and that “there is no competition”. Maybe it’s time for you to step back and create a competitive analysis matrix.

14. AI, changes in social media and VR/AR are rapidly changing how marketers are building their brands, engaging customers and driving sales and lead conversion.

15. There is a big difference between vanity numbers at the top of the funnel or prospect funnel and people who are ready, willing and able to buy (about 3% of the people you contact). Here’s a way to tell the difference

16. The difference and practice of segmentation, targeting and positioning

17. These ten most effective marketing techniques are a diverse group of online and offline strategies. Each technique is most effective when it is working in concert with the others.

18. When to hire a marketer

19. Consultative sales is more about leadership than sales

Most importantly, they don’t understand that branding a service is different from branding a product. That’s, in part, why they are losing patients to non-MDs.

Most entrepreneurs, including doctors, are still stuck in the spray and pray marketing mindset instead of inbound model. The idea is , instead of you finding patients and customers, help them find you.

What’s more, they don’t understand sales operations . The main function of the sales operations team is to smooth the sales process—reduce any friction and incorporate itself to the organization so as to ensure the execution of the sales strategy.

The basic building blocks of medical practice online marketing include building a website, having an search engine optimization (SEO) plan, using social media and managing your online reputation.

Hospital strategy and marketing officers, particularly those who have been recruited from consumer goods and service industries, stare in amazement at board meetings trying to understand why their docs won’t wear the sneakers and compete with the guys down the street. They fail to understand the culture of medical education and the profession that fundamentally places institutional affiliation and engagement way down the totem pole compared to peer acceptance and cooperation.

Another problem occurs when non-sick care entrepreneurs want to hire doctors as advisors, when, in fact, they want them to be salespeople to hospitals and other doctors on commission. The fact is that , in most instances, doctors lack sales knowledge, skills, abilities and competencies to do the job.

The main reason most doctors are not sales and marketing savvy is that they never had to be and they don’t want to be. But, times have changed. Maybe with an attitude adjustment, they’ll be able to get in a quick 18 holes after all.

Image Credit: Unsplash

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.

12 Reasons to Write Your Own Letter of Recommendation

12 Reasons to Write Your Own Letter of Recommendation

GUEST POST from Arlen Meyers, M.D.

Are you stuck? The first step in making a career change is self reflection.

One way to describe yourself and your transferable skills and what you have in mind for the future is to write your own letter of recommendation instead of asking me to do it.

Here are some tips on how to do it. But, why should you do it?

  1. It saves me the trouble of doing it
  2. You know yourself a whole lot better than I do
  3. It makes you think about why somone would want to hire you
  4. It gives you some ideas about where your blind spots and skills gaps are once you have read the job description of a potential job
  5. You will do a much better job than I would
  6. It will give you the chance to use key words that will drive AI resume scanners
  7. You can link to your personal website and other online social media sites that I don’t know about
  8. You can delete social media posts and sites that are not flattering
  9. It will force you to buff up your resume and coordinate it with your Linked profile for a particular job
  10. You can use if for a personal statement, even if they are falling out of favor and a waste of time
  11. It is another way to be kind to yourself and cultivate your inner advocate
  12. It will help you get over your imposter syndrome and tell people about all those transferable skills you have

If you are taking the long view, then write your own obituary. If that’s too heavy a lift at your stage of the game, then just write you own letter of recommendation before you have to request one and ask someone you know, like and trust to send it for you at the appropriate time. I heartily recommend it.

Image Credit: Pixabay

Subscribe to Human-Centered Change & Innovation WeeklySign up here to get Human-Centered Change & Innovation Weekly delivered to your inbox every week.